Sleeve Gastrectomy
Overview
At a Glance
- What it is: About 75–80% of the stomach is removed laparoscopically or robotically, leaving a narrow tube; no intestinal rerouting
- Who it is for: Recommended by the 2022 ASMBS/IFSO guidelines for adults with a BMI of 35 or higher, and considered at a BMI of 30–34.9 with metabolic disease (27.5 or higher for people of Asian descent) (Eisenberg et al., Surgery for Obesity and Related Diseases, 2022)
- Results: Durable weight loss and diabetes improvement in randomized trials with 10 years of follow-up (see Landmark Evidence below)
- Main trade-off: Reflux can develop or worsen, so patients with significant reflux are usually steered toward gastric bypass
- Hospital stay and recovery: Usually one night; most return to desk work in one to two weeks
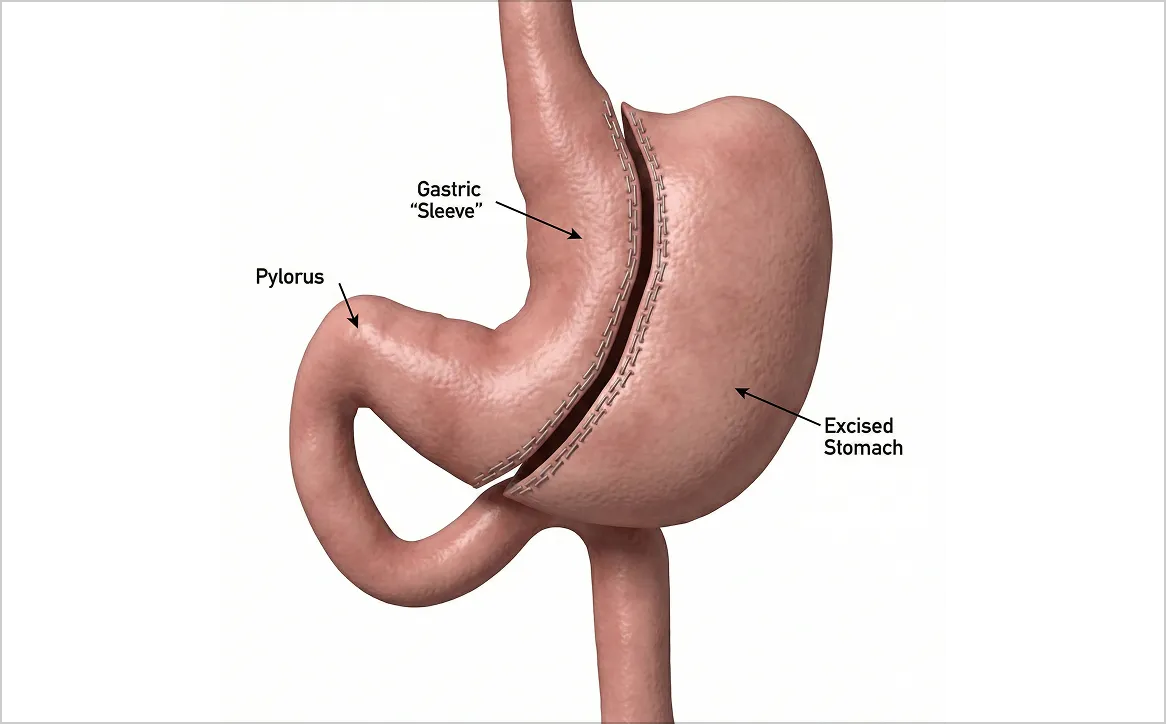
Sleeve gastrectomy is a minimally invasive bariatric (weight-loss) procedure in which a surgeon removes the majority of the stomach along its greater curvature, leaving behind a slim, tube-shaped stomach roughly the size and shape of a banana. The remaining sleeve holds far less food, so patients feel full sooner and eat less.
Just as importantly, the portion of the stomach that is removed (the fundus) is the main site that produces ghrelin, the body's primary "hunger hormone." Removing it lowers ghrelin levels and changes gut hormone signaling (including increases in GLP-1), which reduces appetite and improves blood-sugar control beyond what restriction alone would achieve (Meireles and Saraidaridis, JOMI, 2023; Nuzzo et al., Lancet Gastroenterology & Hepatology, 2021).
It is now the most frequently performed bariatric operation worldwide, in part because it is technically straightforward, does not reroute the intestines, involves no implanted device, carries a lower risk of nutritional deficiency than gastric bypass, and preserves normal access to the stomach and intestines for future endoscopy (Nuzzo et al., Lancet Gastroenterology & Hepatology, 2021). Together with Roux-en-Y gastric bypass, sleeve and bypass account for more than 90% of all bariatric surgeries performed today (Elmaleh-Sachs et al., JAMA, 2023).
If you live in South Florida or are traveling here for surgery, see Gastric Sleeve Surgery in Miami, FL for how the program works from the first visit through long-term follow-up.
How the Procedure Works
Sleeve gastrectomy produces weight loss through two complementary mechanisms:
- Restriction: Removing approximately 75–85% of the stomach reduces its capacity dramatically, so meals become much smaller and satiety comes quickly (Meireles and Saraidaridis, JOMI, 2023; Elmaleh-Sachs et al., JAMA, 2023).
- Hormonal change: The resected fundus contains the oxyntic (P/D1) cells that produce ghrelin. Removing this tissue lowers appetite-stimulating ghrelin, while faster gastric emptying raises satiety hormones such as GLP-1, CCK, and PYY. These changes reduce hunger and improve insulin secretion and blood-sugar control (Meireles and Saraidaridis, JOMI, 2023; Nuzzo et al., Lancet Gastroenterology & Hepatology, 2021).
Because the sleeve changes the body's hormonal "set point" for hunger and metabolism — not just the size of the stomach — it is considered a metabolic operation, not merely a restrictive one.
Benefits
- Significant, durable weight loss — patients typically lose about one-third of their total body weight (Brajcich and Hungness, JAMA, 2020; Puzziferri and Almandoz, JAMA, 2018).
- Improvement or remission of type 2 diabetes — with sustained reductions in fasting glucose and HbA1c and many patients reducing or stopping diabetes medications (Elhag et al., Obesity Surgery, 2025).
- Improvement in high blood pressure, high cholesterol, obstructive sleep apnea, and fatty liver disease (Kheirvari et al., Heliyon, 2020; Elhag et al., Obesity Surgery, 2025).
- Lower complication and malnutrition risk than gastric bypass, with no rerouting of the intestines and no implanted device (Nuzzo et al., Lancet Gastroenterology & Hepatology, 2021).
- Preserved endoscopic access to the stomach and duodenum for future care.
- Minimally invasive laparoscopic or robotic approach, with a short hospital stay (typically 1–2 days) and rapid recovery (Awad, Handbook of Metabolic and Bariatric Surgery, 2022).
Who Is a Candidate
Current guidelines recommend metabolic and bariatric surgery for:
- Adults with a BMI of 40 or higher, or
- Adults with a BMI of 35 or higher with at least one weight-related condition such as type 2 diabetes, hypertension, or sleep apnea, or
- Adults with a BMI of 30–34.9 who have metabolic disease (such as type 2 diabetes) that is not adequately controlled (Elmaleh-Sachs et al., JAMA, 2023).
Lower BMI thresholds apply to patients of Asian descent, who tend to develop metabolic disease at lower weights (Elmaleh-Sachs et al., JAMA, 2023; Kumar et al., SAGES Guidelines, 2025). Candidates should have attempted non-surgical weight management and should be prepared to commit to lifelong dietary, vitamin, and follow-up habits.
Sleeve gastrectomy is an especially good fit for patients without severe acid reflux and without Barrett's esophagus. Patients with severe GERD or Barrett's esophagus are often better served by gastric bypass (Arterburn and Gupta, JAMA, 2018; Di Lorenzo et al., EAES Guidelines, Surgical Endoscopy, 2020).
How the Procedure Is Performed
Sleeve gastrectomy is performed under general anesthesia using a minimally invasive laparoscopic or robotic technique, typically through four to five small incisions. A typical operation takes about one hour and follows these steps (Meireles and Saraidaridis, JOMI, 2023; Takla, JOMI; Awad, Handbook of Metabolic and Bariatric Surgery, 2022):
- The left lobe of the liver is gently retracted to expose the stomach and the junction between the esophagus and stomach (the GE junction).
- The surgeon identifies the GE junction and checks for a hiatal hernia, repairing it if present to reduce the risk of reflux.
- The greater curvature of the stomach is freed by dividing its ligaments and short gastric blood vessels, fully mobilizing the fundus.
- A sizing tube (bougie, commonly 36–40 French) is passed into the stomach to calibrate the width of the new sleeve.
- A surgical stapler is fired sequentially from near the lower stomach (incisura) up toward the GE junction, creating the narrow tubular sleeve and removing the outer portion of the stomach.
- The removed portion of the stomach is extracted through one of the small incisions.
- Many surgeons reinforce the staple line (for example, with an omentopexy) and perform an intraoperative endoscopy or leak test to confirm a straight, leak-free sleeve before completing the operation.
Risks and Considerations
As with any major operation, sleeve gastrectomy carries risks. These are uncommon, and the procedure is considered safe, but patients should understand them (Elmaleh-Sachs et al., JAMA, 2023; Brajcich and Hungness, JAMA, 2020; Kheirvari et al., Heliyon, 2020):
- Staple-line leak — the most serious early complication (roughly 1–7%); intraoperative leak testing is used to minimize this risk.
- Bleeding and, rarely, blood clots (venous thromboembolism).
- Gastric stricture/stenosis — narrowing that can cause food to get stuck (about 1–9%).
- New or worsening acid reflux (GERD) — the most common long-term side effect, occurring in roughly 20–30% of patients and usually managed with medication (Nuzzo et al., Lancet Gastroenterology & Hepatology, 2021).
- Vitamin and mineral deficiencies — less common than after bypass but still require lifelong supplementation.
- Weight regain or insufficient weight loss in a minority of patients, sometimes requiring revision.
Recovery Timeline
Most patients stay in the hospital one to two days and recover quickly on an enhanced-recovery (ERAS) pathway (Awad, Handbook of Metabolic and Bariatric Surgery, 2022):
- Diet progression: clear liquids for roughly the first 1–2 weeks, then pureed/blended foods for weeks 2–4, soft foods at weeks 4–6, and textured/regular foods from about week 6 onward.
- Showering: usually permitted after about 3 days; keep incisions clean and dry.
- Driving: generally after about 10–14 days, once able to brake safely and off narcotic pain medication.
- Return to work: many patients return within about 2 weeks.
- Exercise: light walking begins immediately; gradual return to heavy exercise and heavy lifting from about 6 weeks.
- Other: avoid alcohol for at least 6 weeks, avoid routine NSAIDs early after surgery, and prevent constipation.
Close follow-up — typically phone contact within the first 1–3 weeks, an in-person visit around 6 weeks, then visits at 3, 6, 12, 18, and 24 months — is essential to catch problems early and support long-term success (Awad, Handbook of Metabolic and Bariatric Surgery, 2022).
Long-Term Expectations
Long-term studies show that the majority of weight loss and metabolic benefit occurs within the first year and is largely sustained for many years. In a 9-year study of patients with type 2 diabetes, excess weight loss ranged from about 59% at year 1 to 46% at year 9, with a mean BMI reduction of about 9 kg/m² maintained at 9 years (Elhag et al., Obesity Surgery, 2025). A separate 9-year academic series reported roughly 80% excess weight loss and 31% total weight loss by year 3, remaining satisfactory at 9 years (Ari et al., Obesity Surgery, 2025).
Some weight regain is normal over time — beginning around year 3 in some patients — which makes long-term dietary habits, activity, and follow-up critical (Elhag et al., Obesity Surgery, 2025). Metabolic improvements in blood pressure, cholesterol, triglycerides, and liver enzymes are also sustained long-term (Elhag et al., Obesity Surgery, 2025).
Landmark Evidence
- SLEEVEPASS (Finland, 240 patients, 10 years): median excess weight loss was 43.5% after sleeve versus 50.7% after bypass. Diabetes remission did not differ significantly, esophagitis was more common after sleeve, and Barrett's esophagus was uncommon and similar between groups (Salminen et al., JAMA Surgery, 2022).
- SM-BOSS (Switzerland, 217 patients, 10 years): excess BMI loss was 60.6% after sleeve versus 65.2% after bypass (not significantly different). New reflux developed in 32% of sleeve patients versus 8% after bypass, and 30% of sleeve patients were later converted to another operation, mainly for reflux or weight (JAMA Surgery, 2025).
- STAMPEDE (diabetes, 5 years): 23% of sleeve patients achieved an HbA1c of 6% or less, versus 5% with intensive medical therapy (Schauer et al., New England Journal of Medicine, 2017).
- Survival: Across 17 studies and more than 174,000 people, metabolic and bariatric surgery was associated with a 49% lower risk of death and a median of 6.1 additional years of life compared with non-surgical care. The benefit was greatest in people with type 2 diabetes (Syn et al., The Lancet, 2021).
How It Compares
- Versus gastric bypass: similar diabetes results and somewhat less weight loss over 10 years. Bypass is better for patients with reflux.
- Versus SADI-S and duodenal switch: the sleeve is the first stage of both, and either can be added later if more effect is needed.
- Versus ESG: ESG avoids incisions but produces less weight loss and suits lower BMIs.
More in Bariatric Surgery Procedures
Related procedures: Gastric Bypass, One‑Anastomosis Gastric Bypass, SADI-S, Duodenal Switch, Magnetic Duodeno-Ileal Bypass with Sleeve, Adjustable Gastric Band Surgery. For an overview of all options, see Bariatric Surgery.
Conditions treated: Obesity, Type 2 Diabetes, Sleep Apnea, Metabolic Dysfunction–Associated Steatohepatitis, Metabolic Syndrome, High Blood Pressure.
Why Choose Dr. de la Cruz-Muñoz
Choosing the right surgeon matters as much as choosing the right operation — and for sleeve gastrectomy, that means a surgeon who performs it at high volume, individualizes patient selection, and manages the full spectrum of outcomes, including reflux and the occasional need for revision. Dr. Nestor de la Cruz-Muñoz, MD, FACS, DABOM, brings exactly that combination of experience and judgment.
- High-volume, metabolic and bariatric expertise. Sleeve gastrectomy is the most commonly performed bariatric operation in the world, and outcomes are consistently better in experienced, high-volume hands. Dr. de la Cruz-Muñoz performs the sleeve minimally invasively (laparoscopic and robotic) as a routine, refined operation — not an occasional one.
- Board-certified in both surgery and obesity medicine (DABOM). Dual certification means your care is grounded in the medical science of obesity as a chronic disease, not just the technical operation — so the plan addresses metabolic health, medication strategy, and long-term weight maintenance, not only the day of surgery.
- Physiology-first patient selection. Not every patient is best served by a sleeve. Dr. de la Cruz-Muñoz individualizes the recommendation using objective assessment — including screening for significant acid reflux and hiatal hernia before surgery — because patients with pre-existing GERD or Barrett's esophagus are often better served by gastric bypass. Matching the patient to the right operation is the single most important determinant of long-term success.
- A complete bariatric toolbox. Because he offers the full range of procedures — sleeve gastrectomy, Roux-en-Y gastric bypass, SADI-S, duodenal switch, and revisional/conversion surgery — the recommendation is never driven by what a surgeon happens to offer. If a sleeve is the best first operation but reflux or weight regain later becomes an issue, he can manage it, including conversion to gastric bypass when appropriate.
- Multidisciplinary, lifelong follow-up. Durable results depend on structured aftercare — nutrition, supplementation, activity, and body-composition monitoring to preserve muscle while losing fat. His program is built around long-term partnership, not a single procedure.
- A regional reputation for complex and revisional foregut and metabolic surgery. Patients and physicians across the region refer their most complex cases — including failed prior bariatric and antireflux operations — reflecting a level of trust earned through experience and outcomes.
For patients considering sleeve gastrectomy, this means a careful, honest evaluation of whether the sleeve is truly the best choice for you, an expertly performed minimally invasive operation, and a team committed to your health for years — not just weeks — after surgery.
Dr. de la Cruz-Muñoz has been performing bariatric surgery for over 25 years and has completed more than 9,000 bariatric operations — a volume few surgeons reach.
Research and Publications
Dr. de la Cruz-Muñoz's published and presented work on this topic includes:
- Ribieras AJ, Monzon Canales EJ, Manzur-Pineda K, Cuesta M, Kutlu O, de la Cruz-Muñoz N. Comparison of upper gastrointestinal series and symptom questionnaires with intraoperative diagnosis of hiatal hernia during sleeve gastrectomy. Surgery for Obesity and Related Diseases. 2023.
- Monzon Canales EJ, Ribieras AJ, de la Cruz-Muñoz N. Prospective long-term outcomes in patients undergoing laparoscopic sleeve gastrectomy with and without hiatal hernia repair. ASMBS Annual Meeting, 2024 (Surgery for Obesity and Related Diseases 20(6):S117).
- Invited lecture: “Weight Regain and GERD after Sleeve Gastrectomy.” ASMBS Annual Meeting, Washington, D.C., 2025.
- Ribieras AJ, de la Cruz-Muñoz N, Kutlu O. Comparison of the robotic system and laparoscopy with regards to value in health care delivery in de novo sleeve gastrectomy. IFSO World Congress, Miami, 2022.
Patients in South Florida, and those traveling to Miami for surgery, can find consultation, hospital and recovery details on our gastric sleeve surgery in Miami page.
Authored by Nestor de la Cruz-Muñoz, MD, FACS, DABOM. Last updated November 2026.
Total Body Weight Loss (TBWL) Expectations
Patients can expect to lose approximately 25% of total body weight by 12 months, with sustained loss at 5 years (Elmaleh-Sachs et al., JAMA, 2023). Framed differently, patients typically lose about one-third of their body weight overall — for example, a patient weighing 300 lb can expect to lose roughly 100 lb (Brajcich and Hungness, JAMA, 2020). Sleeve gastrectomy generally produces more weight loss than the adjustable gastric band and somewhat less than gastric bypass (Brajcich and Hungness, JAMA, 2020). In long-term series, total weight loss has been reported around 31% at 3 years (Ari et al., Obesity Surgery, 2025). Individual results vary with adherence to diet, activity, and follow-up.
Expected Metabolic Improvements
- Type 2 diabetes: Significant, sustained reductions in fasting glucose and HbA1c (e.g., HbA1c from ~8.1% before surgery to ~6.8% at 9 years), with 20% of patients in complete remission at 5–9 years and many reducing or stopping diabetes medications (Elhag et al., Obesity Surgery, 2025). In one series, 65.8% of diabetic patients had resolution or major improvement within one year (Meireles and Saraidaridis, JOMI, 2023).
- Hypertension: Resolution or significant improvement in about 68% of patients within one year, with sustained blood-pressure reductions long-term (Meireles and Saraidaridis, JOMI, 2023; Elhag et al., Obesity Surgery, 2025).
- Obstructive sleep apnea: Resolution or significant improvement in about 70% of patients within one year (Meireles and Saraidaridis, JOMI, 2023).
- Lipids and fatty liver: Improvements in triglycerides, HDL, LDL, total cholesterol, and liver enzymes (Elhag et al., Obesity Surgery, 2025; Kheirvari et al., Heliyon, 2020).
Weight Regain Prevention Strategy
Weight regain affects a meaningful minority of patients, with regain beginning around year 3 in some studies and revision rates up to about 20–28% over 7 years (Elhag et al., Obesity Surgery, 2025; Franken et al., Obesity Surgery, 2022). Contributing factors include an initially large sleeve, sleeve dilation over time, rising ghrelin, inadequate follow-up, and maladaptive eating behaviors (Franken et al., Obesity Surgery, 2022). Prevention centers on:
- Lifelong structured follow-up with the bariatric team and dietitian at defined intervals (Awad, Handbook of Metabolic and Bariatric Surgery, 2022).
- A sustained high-protein, fiber-rich, low-calorie eating pattern, eating slowly and chewing thoroughly (Zhao et al., Obesity Surgery, 2025; Coluzzi et al., Obesity Surgery, 2016).
- Consistent physical activity and behavioral support, including attention to emotional eating (Ari et al., Obesity Surgery, 2025).
- Early recognition of regain, so that medical, endoscopic, or revisional options can be considered before regain becomes substantial (Franken et al., Obesity Surgery, 2022).
GERD / Reflux Considerations
Sleeve may worsen reflux in some patients. Those with severe GERD, esophagitis or a large hiatal hernia are usually better served by gastric bypass, which is the most reliable bariatric operation for reflux.
Acid reflux (GERD) is the most important long-term consideration with sleeve gastrectomy. New or worsening GERD occurs in roughly 20–30% of patients and is usually controlled with proton pump inhibitors (Nuzzo et al., Lancet Gastroenterology & Hepatology, 2021). GERD resolves in fewer patients after sleeve (about 25%) than after gastric bypass (about 60%) (Arterburn and Gupta, JAMA, 2018).
Because of this, careful preoperative screening matters: patients with severe GERD or Barrett's esophagus are generally steered toward gastric bypass, while patients with mild or no reflux are excellent sleeve candidates (Arterburn and Gupta, JAMA, 2018; Di Lorenzo et al., EAES Guidelines, Surgical Endoscopy, 2020). Any hiatal hernia found at surgery should be repaired to reduce reflux risk (Arterburn and Gupta, JAMA, 2018). When GERD develops after sleeve, most patients trial medical therapy first; medically refractory cases may be addressed with hiatal hernia repair or conversion to bypass-type anatomy (Kumar et al., SAGES Guidelines, 2025).
Revision Options
A minority of patients require revision after sleeve gastrectomy for weight regain, insufficient weight loss, or refractory GERD (Małczak et al., Obesity Reviews, 2025). Common revisional options include:
- Single-anastomosis duodeno-ileal bypass with sleeve (SADI-S) — ranked highest for additional weight loss in network meta-analyses; best when weight, not reflux, is the main problem, because it keeps the sleeve and does not correct acid reflux (Małczak et al., Obesity Reviews, 2025; Salman et al., World Journal of Surgery, 2024).
- Roux-en-Y gastric bypass (RYGB) — the preferred revision when GERD is the main problem (Franken et al., Obesity Surgery, 2022; Kumar et al., SAGES Guidelines, 2025).
- One-anastomosis gastric bypass (OAGB) and biliopancreatic diversion with duodenal switch (BPD/DS).
- Re-sleeve gastrectomy and endoscopic sleeve gastroplasty in selected cases.
Evidence consistently favors SADI-S for the greatest additional weight loss with comparable complication rates, though the optimal revision remains individualized and debated (Nocca et al., Surgical Endoscopy, 2025; Salman et al., World Journal of Surgery, 2024). All revision candidates should undergo full multidisciplinary re-evaluation (Kumar et al., SAGES Guidelines, 2025).
- Conversion to gastric bypass
- Conversion to SADI‑S
- Conversion to DS
- Endoscopic sleeve reinforcement
- Endoscopic revision for dilation
Body Composition & Muscle Preservation
Rapid weight loss after sleeve gastrectomy includes loss of both fat and lean muscle, making muscle preservation a priority. The cornerstones are adequate protein intake and progressive resistance/physical activity. Guidelines emphasize meeting protein needs (commonly around 1.1 g/kg ideal body weight, often supported with protein supplements in early recovery) alongside a balanced diet, because protein intake frequently falls short after surgery (Coluzzi et al., Obesity Surgery, 2016; Zhao et al., Obesity Surgery, 2025). Combining high-protein nutrition with a gradual return to exercise — walking early, then resistance training as cleared around 6 weeks — helps preserve lean mass while maximizing fat loss (Awad, Handbook of Metabolic and Bariatric Surgery, 2022).
Insurance & Qualification Requirements
Most insurers follow nationally recognized criteria closely aligned with clinical guidelines. Typical requirements include:
- Qualifying BMI: BMI ≥ 40, or BMI ≥ 35 with an obesity-related condition; some programs and payers also cover BMI 30–34.9 with uncontrolled metabolic disease (Elmaleh-Sachs et al., JAMA, 2023).
- Documented non-surgical weight-management attempts prior to referral (Elmaleh-Sachs et al., JAMA, 2023).
- Preoperative nutrition evaluation and mental-health evaluation, plus any additional evaluations required by the surgeon or payer (Elmaleh-Sachs et al., JAMA, 2023).
- Time to surgery is often driven by completion of these preoperative evaluations and the specific health-insurance requirements (Elmaleh-Sachs et al., JAMA, 2023).
(Note: specific supervised-diet durations, documentation windows, and prior-authorization steps vary by payer and plan; the practice team verifies individual coverage.)
Preparing for Surgery (Pre-Op Requirements)
A comprehensive preoperative workup optimizes safety and outcomes (Zhao et al., Obesity Surgery, 2025; Elmaleh-Sachs et al., JAMA, 2023):
- Medical history and physical exam; blood tests; liver and kidney function tests.
- Upper gastrointestinal endoscopy and/or imaging, especially to evaluate for hiatal hernia, GERD, or Barrett's esophagus that could affect procedure choice (Kavanagh et al., Surgical Endoscopy, 2020).
- Nutrition assessment and dietary counseling before surgery, plus mental-health evaluation.
- Cardiac or pulmonary clearance when indicated by comorbidities.
- Correction of micronutrient deficiencies and initiation of a preoperative diet as directed.
- Preoperative fasting (ERAS): typically solids until 6 hours before surgery and clear liquids up to 2 hours before (≤200 mL), unless an individual condition requires modification (Pereira et al., Brazilian Guide to Nutrition in Bariatric and Metabolic Surgery, Langenbeck's Archives of Surgery, 2023).
Post-Op Nutrition Overview
Nutrition advances in stages to protect the healing sleeve (Awad, Handbook of Metabolic and Bariatric Surgery, 2022; Coluzzi et al., Obesity Surgery, 2016):
- Weeks 0–1 (to ~2): clear/full liquids.
- Weeks 2–4: pureed/blended foods.
- Weeks 4–6: soft, easy-to-chew foods.
- Week 6 onward: textured, regular foods.
Lifelong priorities include prioritizing protein at every meal (often with protein supplements early on), eating slowly and chewing well, staying hydrated between meals, meeting minimum carbohydrate and fat needs, and taking daily multivitamin and micronutrient supplementation (including vitamin B12, folate, iron, vitamin D, calcium, and others) to prevent deficiencies (Elmaleh-Sachs et al., JAMA, 2023; Nuzzo et al., Lancet Gastroenterology & Hepatology, 2021; Zhao et al., Obesity Surgery, 2025).
Post-Op Activity & Exercise Guidance
- Immediately: early mobilization and daily walking to reduce clot risk and speed recovery (Awad, Handbook of Metabolic and Bariatric Surgery, 2022).
- Days 10–14: many patients resume driving (once off narcotics and able to brake safely) and return to desk/light work (Awad, Handbook of Metabolic and Bariatric Surgery, 2022).
- ~6 weeks: gradual return to heavy exercise, heavy lifting, and resistance training once cleared (Awad, Handbook of Metabolic and Bariatric Surgery, 2022).
- Ongoing: consistent aerobic plus resistance activity supports fat loss, muscle preservation, and long-term weight maintenance.
Special Considerations for International Patients
International patients should plan to stay in Miami for approximately one week. All follow-ups can be completed virtually. Pre-operative testing is grouped into the first days after arrival, and you will leave with a written diet and vitamin plan to follow at home.
Quick Procedure Details
Coverage generally requires documented qualifying BMI and comorbidities, prior non-surgical weight-management attempts, and completed preoperative nutrition and mental-health evaluations; timing to surgery often depends on completing these payer-required evaluations (Elmaleh-Sachs et al., JAMA, 2023). Supervised-diet durations, documentation windows, and prior-authorization rules differ by plan — the practice verifies benefits and manages authorization for each patient.
Featured Procedures












Conditions












FAQ
Most patients go home after one night and return to normal daily activities within one to two weeks. Desk work usually resumes in one to two weeks and physical work in four to six weeks. Walking starts the day of surgery, and structured exercise usually begins at four to six weeks. The diet advances from liquids to pureed and soft foods, with regular textures at about six to eight weeks.
Most patients have far less hunger after surgery, because the operation lowers the hunger hormone ghrelin and raises fullness hormones. Many describe the constant "food noise" going quiet for the first time in years.
Some hunger usually returns gradually over the following months and years, which is normal. Eating protein first, keeping a regular meal schedule and staying in follow-up help keep appetite manageable.
Some weight regain after bariatric surgery is common, and it is treatable. It is not a sign of failure. The first step is an evaluation to find the cause, which may include an endoscopy, labs and a review of eating patterns.
Depending on the cause, options include nutrition and behavioral support, GLP-1 medications, endoscopic procedures such as TORe, or revisional surgery. Staying in regular follow-up is the best way to catch regain early.
Most patients describe sleeve gastrectomy pain as mild to moderate, similar to muscle soreness or pressure under the ribs. The discomfort comes from the laparoscopic incisions and the stomach reshaping—not from large cuts or internal rerouting. Pain improves significantly within 48–72 hours and is usually well‑controlled with non‑opioid medications. Walking every hour reduces gas pressure and speeds recovery.
Sleeve gastrectomy is considered safe and is the most common bariatric operation worldwide, but like any surgery it has risks. The most serious early risk is a staple-line leak (about 1–7%); others include bleeding, blood clots, and narrowing (stricture). The most common long-term issue is acid reflux, affecting about 20–30% of patients and usually controlled with medication. Vitamin and mineral deficiencies are less common than after gastric bypass but require lifelong supplements (Elmaleh-Sachs et al., JAMA, 2023; Nuzzo et al., Lancet Gastroenterology & Hepatology, 2021).
Most patients stay in the hospital 1–2 days and recover quickly. Diet advances in stages: liquids for about the first 1–2 weeks, pureed foods for weeks 2–4, soft foods for weeks 4–6, and regular textured foods from about week 6. Many people drive again around 5 days and return to work within about 2 weeks, with a gradual return to heavy exercise and lifting at about 6 weeks. Lifelong vitamins, high-protein nutrition, and scheduled follow-up visits are key to long-term success (Awad, Handbook of Metabolic and Bariatric Surgery, 2022).
There is no single best operation. The choice depends on your BMI, whether you have reflux or a hiatal hernia, how severe your diabetes is, your eating patterns, prior surgeries and long-term goals. Sleeve gastrectomy and gastric bypass are the most common procedures. Gastric bypass is preferred for significant reflux. SADI-S and duodenal switch offer the greatest weight loss and diabetes control for higher BMIs, with a greater need for vitamin monitoring. Your surgeon will recommend the best fit after a full evaluation.
It depends on your goals and health. The duodenal switch produces the most weight loss and diabetes remission, but it requires more intensive lifelong nutritional monitoring and can cause more frequent bowel movements. Sleeve gastrectomy is simpler, and gastric bypass is preferred for reflux. For patients with a very high BMI or severe diabetes, DS or SADI-S may be the best option. Your surgeon will help you weigh the benefits and trade-offs based on your anatomy and medical history.
Yes. You can complete your initial gastric sleeve consultation virtually, including a review of your medical history, a discussion of whether the sleeve is right for you — particularly if you have reflux — surgical planning and insurance verification. Many pre-operative steps can also be completed remotely before you come to Miami for surgery.
Most patients spend one night in the hospital and return to normal daily activities within one to two weeks. Many go back to desk work in one to two weeks, while physical jobs may need four to six weeks. Structured exercise typically begins at four to six weeks. The diet progresses from clear liquids to protein shakes, pureed and soft foods, reaching regular textures at about six to eight weeks.
The best operation depends on your BMI, reflux or hiatal hernia, diabetes severity, eating patterns, prior surgeries, medications and long-term goals. Sleeve gastrectomy and gastric bypass are the most common choices; gastric bypass is preferred for reflux, and SADI-S or duodenal switch for higher BMIs or advanced diabetes. Your surgeon will recommend the best fit after a full evaluation.
Yes. Many Florida insurance plans cover sleeve gastrectomy when you meet their criteria, including Medicare, Medicaid and many commercial plans. Coverage varies by policy, and some employers exclude bariatric surgery. Most plans require documentation of BMI and related conditions, nutrition visits and medical clearance. Our office verifies your benefits and helps you complete requirements for approval.
Most patients lose about 60–70% of their excess weight within 12–18 months. Results depend on starting weight, adherence to nutrition and activity plans, and metabolic factors. Some patients regain part of the weight over the long term; follow-up and, when needed, medications or revision surgery help address that. Your surgeon can give a personalized estimate and compare the sleeve with other options.
An experienced, high-volume program offers minimally invasive sleeve gastrectomy with careful evaluation for reflux and hiatal hernia beforehand — the main factors that determine whether a sleeve or bypass is the better choice. The program also handles the full range of sleeve revisions if they are ever needed, along with long-term nutrition follow-up and virtual care for out-of-town patients. Dr. de la Cruz-Muñoz has performed more than 9,000 bariatric operations over more than 25 years — a volume few surgeons reach.
Sleeve gastrectomy removes about 75–80% of the stomach, leaving a narrow, banana-shaped tube. The smaller stomach holds less food, and removing the upper stomach lowers levels of ghrelin, the hunger hormone, which reduces appetite. It does not reroute the intestines. The sleeve is the most commonly performed bariatric operation worldwide, offers strong weight loss and improvement in diabetes, and requires lifelong vitamins. It can worsen reflux in some patients.
Yes. Sleeve gastrectomy is one of the safest bariatric procedures, with low rates of serious complications when performed by an experienced surgeon at an accredited center. Possible risks include bleeding, leaks along the staple line, blood clots and, later, reflux, strictures and nutritional deficiencies. Overall, the risk of serious complications is similar to common operations such as gallbladder removal, and the health risks of untreated severe obesity are generally greater.
Blogs




Guides




Before & After Cases


Patient Stories
Ammy A. underwent sleeve gastrectomy in May 2026 and has experienced a remarkable transformation in both her health and quality of life. She reduced her weight from 232 pounds to 150 pounds, losing 82 pounds following surgery. Her body fat percentage improved from 44.3% to 30%, her BMI decreased to 26, and her visceral fat area returned to a normal range.
Ammy describes bariatric surgery as one of the best decisions she has ever made and wishes she had pursued treatment sooner. Before surgery, everyday activities could feel exhausting and frustrating. Today, she enjoys exercising, walking comfortably, and participating fully in daily life without the limitations obesity once imposed.
She also emphasizes that weight loss surgery is about far more than appearance. For her, the procedure improved physical health, mental well-being, energy levels, self-confidence, and overall happiness. Ammy enthusiastically recommends Dr. Nestor de la Cruz-Muñoz and his team, highlighting their ongoing support and commitment to patient care throughout the journey.
Video in Spanish.

Mary J. underwent sleeve gastrectomy with Dr. Nestor de la Cruz-Muñoz and experienced remarkable improvements in mobility, pain, and overall quality of life within days of surgery.
Before surgery, she depended on a walker to get around and often needed to sit after walking short distances. At her follow-up visit just days after her procedure, she was able to walk independently from the parking lot into the office without assistance. She also noticed early improvements in knee discomfort and daily movement.
Mary describes feeling stronger, more independent, and more optimistic about the future. While she understands that sustained success will require continued hydration, exercise, and healthy habits, she is already experiencing meaningful improvements that have motivated her to continue her journey.
Her advice to others considering bariatric surgery is simple: don't let fear stop you from improving your health. She encourages patients to pursue treatment for themselves and their future, explaining that the procedure was easier than she expected and that she quickly noticed positive changes in her life.

Dr. DeLaCruz Munoz help changed my life for the better after having gastric sleeve surgery in 2012. He is intuitive, well-versed, caring, passionate, and an overall outstanding medical doctor. I love his work ethics