Sleeve Gastrectomy to Magnetic Duodeno-Ileostomy (MagDI) Conversion

Overview
Sleeve gastrectomy (SG) is the most commonly performed bariatric operation in the world, but more than 20% of patients eventually need a revisional procedure for weight regain, inadequate weight loss, or reflux (Małczak et al., Obesity Reviews, 2025). When the problem is weight rather than reflux, adding a malabsorptive duodeno-ileal bypass to the existing sleeve — the SADI-S approach — produces among the largest additional weight loss of mainstream sleeve revisions (Małczak et al., 2025; Salman et al., World Journal of Surgery, 2024). The magnetic duodeno-ileostomy, or MagDI, is a new way of creating that same duodeno-ileal diversion without staples or sutures.
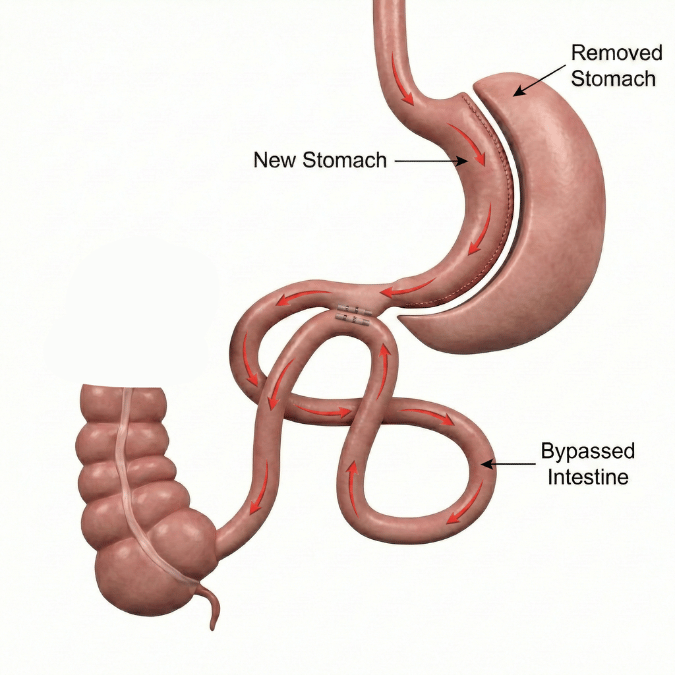
Instead of a hand-sewn or stapled anastomosis, MagDI uses a magnetic compression anastomosis (MCA) device (the Magnet Anastomosis System / GT Metabolic Solutions MagDI System): two linear magnets are placed endoscopically — one in the first part of the duodenum, one in the ileum — and aligned with laparoscopic assistance. Over the following weeks the magnets gradually fuse the two bowel walls into a patent, sutureless side-to-side duodeno-ileal anastomosis and are then passed naturally (Gagner et al., SOARD, 2024; Cadière et al., J Gastrointest Surg, 2024). The rationale is that avoiding a cut-and-sewn anastomosis may reduce leak, bleeding, and stricture — the most feared anastomotic complications of conventional bypass surgery (Gagner et al., 2024).
Because a sleeve already exists, MagDI can be performed either concurrently with a sleeve (MagDI + SG) or after a prior sleeve as a conversion (MagDI-after-SG) (Gagner et al., 2024). This page covers the conversion use — adding a MagDI to a patient who already has a sleeve. It is essential to be candid: the published experience is small (tens of patients across a handful of centers), follow-up is short (6–12 months in most series), and the conversion-after-sleeve subgroup specifically has shown more modest early weight loss than the concurrent operation (Gagner et al., 2024; Chiappetta et al., Obesity Surgery, 2026). MagDI should therefore be understood as a promising but investigational option, offered in experienced centers and ideally within a structured program or study (Chiappetta et al., 2026).
How the Procedure Works
MagDI produces weight loss by adding a malabsorptive, hormone-altering intestinal bypass to the restriction already provided by the existing sleeve. Two magnets are brought together — one in the duodenum just past the stomach outlet, one in a loop of ileum — and magnetic compression creates a side-to-side channel (a "bipartition") between the duodenum and the distal small bowel (Cadière et al., 2024). Food then splits between the normal route and this new shortcut to the ileum: in an isotopic transit study, roughly 19% of an ingested meal passed directly through the ileal loop after the bipartition (Cadière et al., 2024). Diverting a portion of food past most of the small intestine reduces calorie and nutrient absorption and triggers favorable gut-hormone changes, the same physiologic principles that drive weight loss and diabetes improvement in SADI-S and the duodenal switch (Gagner et al., 2024). The magnets are placed 250 cm proximal to the ileocecal valve in the reported technique, a length chosen to balance weight loss against malnutrition risk (Cadière et al., 2024). Because the pylorus is preserved and no bowel is divided, the approach avoids the mesenteric defects and marginal-ulcer risk associated with gastric bypass (Gagner et al., 2024).
Benefits
- Incisionless, sutureless anastomosis — no staple line or suture line on the new connection, with the goal of reducing leak, bleeding, and stricture; across the early studies there were no device-related leaks, bleeds, obstructions, infections, or deaths (Gagner et al., 2024; Cadière et al., 2024).
- Adds a malabsorptive mechanism to a failed sleeve — the same duodeno-ileal diversion physiology that makes SADI-S the most effective sleeve revision, delivered with a different anastomotic technique (Gagner et al., 2024; Małczak et al., 2025).
- Pylorus-preserving — keeping the natural stomach outlet reduces dumping and the marginal-ulcer risk seen with gastric bypass (Gagner et al., 2024).
- Fewer and milder adverse events when done after a prior sleeve — in the multicenter series, the MagDI-after-SG group had significantly fewer adverse events than the concurrent group, and most events were minor (Clavien-Dindo grade I–II) (Gagner et al., 2024).
- Early metabolic improvement — all patients with type 2 diabetes improved in the first multicenter study, and Italian data showed early HbA1c reductions (Gagner et al., 2024; Chiappetta et al., 2026).
- High technical feasibility — magnet placement, confirmed patent anastomosis, and spontaneous magnet passage were achieved in 100% of patients in the first series (Gagner et al., 2024).
Who Is a Candidate
MagDI conversion is being studied in patients with a prior sleeve gastrectomy who have:
- Weight regain or inadequate weight loss after the sleeve and a BMI in the studied range (roughly 35–50 kg/m²), who want additional malabsorptive weight loss (Gagner et al., 2024).
- No significant gastroesophageal reflux — as with SADI-S, a duodeno-ileal diversion does not correct reflux, so significant GERD generally directs a patient to a Roux-en-Y gastric bypass instead (Gagner et al., 2024; Chiappetta et al., 2026).
- Type 2 diabetes or other metabolic disease, where the malabsorptive physiology is advantageous — including selected patients with class I obesity and T2DM in the early European experience (Chiappetta et al., 2026).
- Willingness to commit to strict lifelong supplementation and monitoring, because this is a malabsorptive operation (Chiappetta et al., 2026).
- Willingness to accept the uncertainty of a newer, investigational, device-based procedure with limited numbers and short follow-up, ideally within a structured program or registry (Chiappetta et al., 2026).
A patient whose main goal is the largest, most proven, most durable additional weight loss after a sleeve is generally better served today by a conventional conversion SADI-S, which has far more supporting data (Esparham et al., SOARD, 2026; Małczak et al., 2025). A thorough upper GI and endoscopic evaluation is essential to assess the sleeve and rule out reflux before choosing this pathway.
How the Procedure Is Performed
The procedure is a hybrid endoscopic-laparoscopic operation performed under general anesthesia. Two linear magnets are delivered endoscopically — a proximal magnet into the first part of the duodenum and a distal magnet into the ileum (placed 250 cm proximal to the ileocecal valve) — and then aligned with laparoscopic assistance so the two magnets lock together (Gagner et al., 2024; Cadière et al., 2024). No bowel is cut and no anastomosis is sewn or stapled during the operation; instead, the paired magnets apply continuous compression that, over the following weeks, fuses the two bowel walls into a patent channel. The magnets then detach and are passed naturally in the stool — at a median of about 43 days in the reported series (Cadière et al., 2024). In the conversion setting, the existing sleeve is left in place (and inspected), so the operation adds the duodeno-ileal bipartition to the prior sleeve. Reported median operative time for the concurrent operation was about 161 minutes, and because this is a novel device-based technique, it should be performed only by surgeons trained in the system at experienced centers (Cadière et al., 2024; Chiappetta et al., 2026).
Our GT Metabolic Duodenoileostomy Animation: Step-by-Step Magnetic Anastomosis shows how the magnetic connection forms, step by step.
Risks and Considerations
MagDI's central selling point is a favorable anastomotic safety profile, and the early data support that — but the numbers are small and the follow-up is short, so risk counseling must be candid. Across the first multicenter study (43 patients) there were no device-related serious adverse events — no anastomotic leak, bleeding, obstruction, infection, or death — and the 1-year French feasibility series (10 patients) likewise reported no device-related serious adverse event with all anastomoses patent at one year (Gagner et al., 2024; Cadière et al., 2024). Most adverse events were minor (Clavien-Dindo grade I–II), and were significantly fewer in the MagDI-after-SG (conversion) group than in the concurrent-sleeve group (Gagner et al., 2024).
The more important long-term risk is nutritional, because — like any duodeno-ileal diversion — MagDI bypasses the duodenum and proximal small bowel where iron, calcium, and fat-soluble vitamins are chiefly absorbed; the Italian multicenter group explicitly cautioned that vigilance for nutritional deficiencies remains essential (Chiappetta et al., 2026). By analogy to revisional SADI-S, expected longer-term issues include deficiencies of fat-soluble vitamins, iron, B12, folate, and zinc, along with diarrhea/steatorrhea and, in a minority, protein-calorie malnutrition — all requiring strict lifelong supplementation and monitoring (Esparham et al., 2026). The honest bottom line: the magnetic technique appears to lower anastomotic risk in early studies, but the malabsorptive nutritional risk is intrinsic to the bypass itself and is not eliminated by the magnets, and long-term safety data simply do not yet exist (Chiappetta et al., 2026).
Recovery Timeline
Recovery is easier than with other minimally invasive duodeno-ileal procedures: the operation is usually performed as an outpatient, followed by a staged diet progression (Cadière et al., 2024). A feature unique to MagDI is that the anastomosis forms gradually over several weeks while the magnets remain in place, then the magnets pass naturally in the stool (median ~43 days) — patients are counseled about this expected process (Cadière et al., 2024). Early, progressive walking reduces clot risk, and patients begin a strict lifelong supplementation and follow-up routine immediately.
Long-Term Expectations
Long-term expectations cannot yet be stated with confidence — this is the key honest message of the page. The published MagDI experience extends only to about 1 year, and the conversion-after-sleeve subgroup specifically showed modest early weight loss (see TBWL below), far less than the concurrent sleeve-plus-MagDI operation at the same 6-month mark (Gagner et al., 2024). The Italian multicenter group concluded that results must be interpreted cautiously given small samples, short follow-up, and a heterogeneous cohort, and that larger studies with longer follow-up and direct comparison to established revisions are required (Chiappetta et al., 2026). For a realistic sense of what a well-functioning duodeno-ileal diversion can achieve after a sleeve over the long run, the mature SADI-S conversion data are the best available proxy: roughly 22–24% total weight loss maintained through 5 years (Esparham et al., 2026) — but whether MagDI will match that durability is unproven.
More in Sleeve Gastrectomy Revisions
Related procedures: Re-Sleeve Gastrectomy, Hiatal Hernia Repair After Sleeve Gastrectomy, Gastric Sleeve Stricture Management, Sleeve Gastrectomy to Roux-en-Y Gastric Bypass Conversion, Sleeve Gastrectomy to SADI-S Conversion, Sleeve Gastrectomy to Duodenal Switch Conversion. Related primary operations: Sleeve Gastrectomy, Magnetic Duodeno-Ileal Bypass with Sleeve. For an overview of all options, see Revisional Bariatric Surgery.
Conditions treated: Weight Regain, Inadequate Weight Loss, Stomach Narrowing (Stricture) After Bariatric Surgery, Hiatal Hernia & Paraesophageal Hernia.
Why Choose Dr. de la Cruz-Muñoz
Dr. Nestor de la Cruz-Muñoz is a nationally recognized bariatric and metabolic surgeon with extensive experience in advanced revisional procedures and emerging technologies such as magnetic anastomosis. He applies that expertise with the goal of a safe sleeve revision and precise MagDI creation.
Dr. de la Cruz-Muñoz has been performing bariatric surgery for over 25 years and has completed more than 9,000 bariatric operations — a volume few surgeons reach.
Total Body Weight Loss (TBWL) Expectations
Expectations should be set honestly and conservatively. In the first multicenter study, the MagDI-after-SG (conversion) group lost about 8 kg with 17.4% excess weight loss at 6 months. This is meaningful but modest (although weight loss appears better with the larger, 50 mm magnets that we are using), whereas the concurrent MagDI + SG group lost far more (about 34 kg, 66.2% EWL), reflecting the added effect of a fresh sleeve (Gagner et al., 2024). The concurrent operation at 1 year reached about 34% total weight loss (Cadière et al., 2024), but that figure includes a new sleeve and does not apply to a patient who already has one. For the conversion use specifically, patients should expect additional weight loss on top of their sleeve, the long-term magnitude of which is not yet established; the comparable conventional operation (conversion SADI-S) yields roughly 22–24% total weight loss at 1–5 years (Esparham et al., 2026). Individual results depend on starting BMI, residual sleeve anatomy, the common-channel length, adherence, and factors still being studied.
Expected Metabolic Improvements
Early metabolic results are encouraging. All patients with type 2 diabetes improved in the first multicenter MagDI study, and the Italian multicenter experience reported early reductions in HbA1c, consistent with the strong glycemic effect expected from a duodeno-ileal diversion (Gagner et al., 2024; Chiappetta et al., 2026). By analogy, conventional revisional SADI-S achieves roughly 69% diabetes remission along with meaningful improvement in hypertension, hyperlipidemia, and sleep apnea (Esparham et al., 2026). Whether MagDI will match those remission rates over the long term is not yet proven, but the metabolic rationale is the same and the early signal is favorable.
Weight Regain Prevention Strategy
Durable results require the same lifelong plan as any malabsorptive conversion: protein-prioritized nutrition, strict daily supplementation, regular physical activity, and multidisciplinary behavioral follow-up. Because MagDI is new and its long-term durability is unknown, close structured follow-up is especially important, and anti-obesity medications (including GLP-1 therapy) can be layered on when appropriate to protect results.
GERD / Reflux Considerations
As with SADI-S, a duodeno-ileal diversion does not reliably correct reflux, and significant pre-existing GERD generally directs a patient toward a Roux-en-Y gastric bypass instead (Gagner et al., 2024; Chiappetta et al., 2026). A pre-conversion endoscopy and reflux assessment are essential, and patients whose dominant problem is reflux should not be offered a MagDI. On the positive side, preserving the pylorus and avoiding a bile-exposed anastomosis near the esophagus means the technique shares the generally favorable reflux profile of SADI-S relative to procedures like OAGB (Salman et al., 2024).
Revision Options
MagDI is one of several ways to add a duodeno-ileal diversion to a failed sleeve; the established alternatives have far more supporting evidence and should be presented alongside it:
- Sleeve → MagDI (this page) — an emerging, incisionless/sutureless magnetic version of the duodeno-ileal bypass; favorable early anastomotic safety but investigational, with small numbers and short follow-up (Gagner et al., 2024; Chiappetta et al., 2026).
- Sleeve → SADI-S — the conventional, stapled single-anastomosis duodeno-ileal bypass; ranked highest for additional weight loss among sleeve revisions, with mature 5-year data (Małczak et al., 2025; Esparham et al., 2026).
- Sleeve → Roux-en-Y gastric bypass — the gold standard when reflux is the dominant problem; more modest additional weight loss than SADI-S (Rivero-Moreno et al., J Laparoendosc Adv Surg Tech, 2026).
- Sleeve → one-anastomosis gastric bypass (OAGB) — strong weight loss but more associated bile reflux than SADI-S (Ahmed et al., Obesity Surgery, 2024).
- Sleeve → BPD/DS — the classic two-anastomosis duodenal switch for higher-BMI patients; technically more complex.
See the Revisional Bariatric Surgery hub and the dedicated sub-pages for each pathway.
Body Composition & Muscle Preservation
As with any weight-loss operation — and especially a malabsorptive one — a portion of the weight lost is lean mass, so protecting muscle is critical. A high daily protein intake (generally ≥60–80 g/day, and often higher after a malabsorptive procedure), resistance training, and body-composition monitoring help ensure the weight lost is predominantly fat, preserving metabolic rate and supporting durable results. Because a duodeno-ileal diversion malabsorbs protein and fat, meeting protein targets and monitoring albumin are especially important.
Insurance & Qualification Requirements
Coverage is the single biggest practical barrier for this procedure. The magnetic duodeno-ileostomy is a new, device-based technique that most payers will consider investigational or experimental, and it is unlikely to be covered as a standard revisional benefit; access is often limited to centers participating in trials, registries, or specific device programs. Beyond that, revision coverage generally requires documentation of the original sleeve, objective evidence of weight regain or inadequate weight loss (and absence of untreated reflux), and a repeat preoperative work-up, and some policies will not cover a second weight-loss procedure performed for weight-loss failure. Our team reviews current coverage and program availability and handles the documentation needed to pursue authorization.
Preparing for Surgery (Pre-Op Requirements)
Preparation mirrors a conversion SADI-S work-up. This includes an upper GI contrast study and endoscopy to assess the sleeve, rule out significant reflux or esophagitis (which would redirect the patient to a gastric bypass), and confirm the indication; a complete multidisciplinary evaluation (nutritional, behavioral/psychosocial, and medical optimization); thorough baseline nutritional labs (fat-soluble vitamins, iron studies, B12, folate, zinc, albumin) with correction of any pre-existing deficiencies; smoking cessation; and cardiac, pulmonary, and sleep-apnea evaluations as indicated. Because MagDI is investigational, informed-consent counseling must explicitly cover its newness, the limited and short-term evidence base, the gradual magnet-fusion-and-passage process, and the conventional alternatives (Chiappetta et al., 2026).
Post-Op Nutrition Overview
Patients follow the staged bariatric diet (clear liquids → full liquids → pureed → soft → regular textures) over several weeks, with emphasis on high protein intake, hydration, and small portions. Because MagDI is a malabsorptive operation that diverts food past the duodenum and proximal small bowel, lifelong supplementation and routine lab monitoring are required — including fat-soluble vitamins (A, D, E, K), iron, calcium, vitamin B12, folate, and zinc — with vigilance for anemia, hypoalbuminemia, and protein-calorie malnutrition (Chiappetta et al., 2026; Esparham et al., 2026). Regular dietitian follow-up is essential.
Post-Op Activity & Exercise Guidance
Early, progressive walking reduces clot risk and speeds recovery. Patients gradually resume normal activity over the first few weeks, avoid heavy lifting during initial healing, and transition into a combined aerobic and resistance-training program to preserve lean muscle mass and support durable weight loss — particularly important given the malabsorptive nature of this procedure.
Special Considerations for International Patients
Sleeve-to-MagDI conversion uses a newer magnetic technique, so a careful virtual review of your sleeve history, reflux symptoms and labs comes first. Travelers usually stay approximately one week, with nutrition monitoring coordinated with a local physician.
Quick Procedure Details
Because this is a novel device-based procedure, most plans will classify it as investigational/experimental and may deny coverage outright; availability is frequently tied to specific centers or programs. Standard revision requirements (documentation of the original sleeve, objective proof of failure, repeat supervised evaluation) also apply, and some policies exclude a second weight-loss procedure entirely. Our office verifies current benefits and program availability and builds the documentation needed to pursue authorization.
Featured Procedures










Conditions








FAQ
A MagDI (magnetic duodeno-ileostomy) creates the same kind of malabsorptive duodeno-ileal bypass as a SADI-S, but instead of cutting and stapling the bowel, it uses two magnets placed endoscopically and aligned laparoscopically to form a sutureless side-to-side anastomosis that develops gradually over several weeks, after which the magnets pass naturally (Gagner et al., SOARD, 2024; Cadière et al., J Gastrointest Surg, 2024). The goal is to lower the risk of leak, bleeding, and stricture. The key difference is evidence: SADI-S has mature 5-year data, while MagDI is new, with small numbers and short follow-up (Esparham et al., SOARD, 2026; Chiappetta et al., Obesity Surgery, 2026).
In the early studies, the magnetic anastomosis itself had a strong safety signal — no device-related leaks, bleeds, obstructions, infections, or deaths across the first multicenter series, and all anastomoses were patent at one year in the French feasibility study (Gagner et al., SOARD, 2024; Cadière et al., J Gastrointest Surg, 2024). However, these are small studies with short follow-up, and the malabsorptive nutritional risks of any duodeno-ileal bypass — vitamin deficiencies and possible protein malnutrition — still apply and require lifelong monitoring (Chiappetta et al., Obesity Surgery, 2026). It should be viewed as promising but investigational.
The conversion-specific data are early and modest: in the first multicenter study, patients who had a MagDI after a prior sleeve lost about 8 kg (17.4% excess weight loss) at six months, considerably less than patients who had a sleeve and MagDI together (Gagner et al., SOARD, 2024). Long-term conversion results are not yet established. For comparison, the conventional equivalent — conversion SADI-S — produces roughly 22–24% total weight loss maintained through five years (Esparham et al., SOARD, 2026).
Yes — common revisions include sleeve → bypass or sleeve → SADI -S.
Early results suggest weight loss similar to SADI-S, with many patients losing roughly 65–80% of excess weight, along with improvements in diabetes and other metabolic conditions. MagDI is a newer procedure, so long-term results are still being collected. When used as a revision after a sleeve, it can provide meaningful additional weight loss. Lifelong vitamins and lab monitoring are required.