Magnetic Duodeno-Ileal Bypass with Sleeve (MagDI + Sleeve)

Overview
At a Glance
- What it is: A sleeve gastrectomy plus a side-to-side duodeno-ileal connection formed by magnets rather than staples or sutures
- Who it is for: Selected adults meeting bariatric criteria, particularly with type 2 diabetes, who understand it is an emerging procedure
- Results: Promising early safety, weight and diabetes results (see Landmark Evidence below)
- Main trade-off: Long-term data do not yet exist
- Hospital stay and recovery: Usually a few days in the hospital
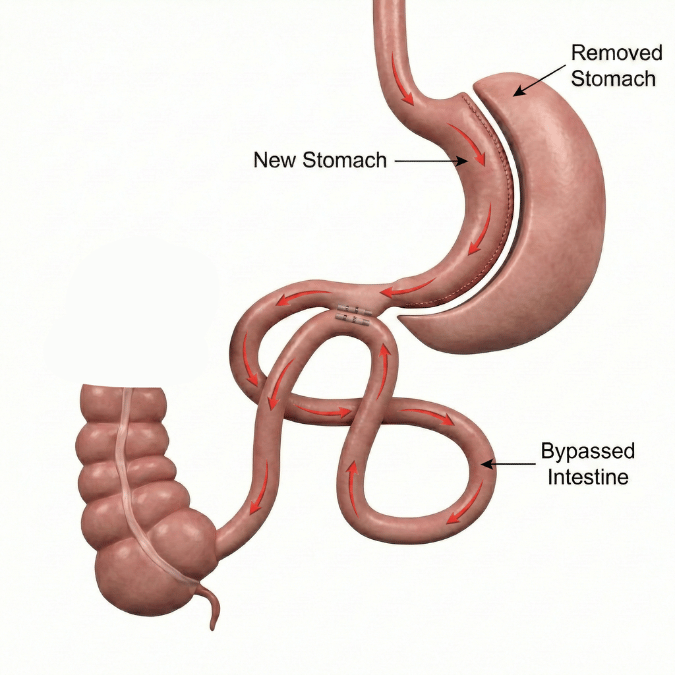
Magnetic duodeno-ileostomy with sleeve gastrectomy (MagDI + SG) is a newer metabolic and bariatric operation that pairs a standard sleeve gastrectomy with a second intestinal connection — but with a key innovation: the new connection between the duodenum and the ileum is created by two self-aligning magnets rather than by staples or stitches (Surgical Endoscopy, 2023; Journal of Gastrointestinal Surgery, 2024). The magnets are placed with a combination of endoscopy and minimally invasive (laparoscopic) assistance. Over several days they gently fuse the two segments of bowel together, forming a smooth, natural opening (a "compression anastomosis"), and the magnet pair is then passed out of the body naturally (Surgical Endoscopy, 2023; Obesity Surgery, 2024).
This technique is a magnetic variation on the concept behind the duodenal switch and SADI-S, using a side-to-side "bipartition" that partially redirects food to the lower intestine while still preserving some flow through the normal path — which helps protect absorption of vitamins and reduces diarrhea (Obesity Surgery, 2024). It is important to understand that MagDI + SG is an emerging, early-stage procedure. Current evidence comes from small, early feasibility and safety studies rather than large long-term trials, and it should be considered investigational (Surgery for Obesity and Related Diseases, 2024; Journal of Gastrointestinal Surgery, 2024).
Patients whose main goal is better control of diabetes and other metabolic disease can learn more on Metabolic Surgery in Miami, FL.
How the Procedure Works
MagDI + SG produces weight loss and metabolic improvement through several mechanisms:
• Restriction: The sleeve gastrectomy removes most of the stomach, leaving a narrow tube so meals feel satisfying with smaller portions (Surgical Endoscopy, 2023).
• Partial malabsorption (bipartition): The magnet-created connection links the duodenum (just past the stomach) to a loop of ileum about 250 cm from the end of the small intestine, redirecting a portion of food to the lower bowel and reducing calorie and nutrient absorption. Because the normal intestinal path is preserved as well, some food still travels the usual route — in one study about 19% of a meal passed directly through the ileal loop (Journal of Gastrointestinal Surgery, 2024).
• Hormonal/metabolic change: Delivering nutrients to the lower intestine enhances gut hormone signaling that improves blood-sugar control, often rapidly (Surgical Endoscopy, 2023).
• Sutureless connection: Because no cut, staple, or stitch is made at the new intestinal connection, the technique is designed to avoid the leak, bleeding, and infection that can occur at a conventional anastomosis (Obesity Surgery, 2024).
Benefits
Strong early weight loss when combined with sleeve gastrectomy. In a multicenter study, patients undergoing concurrent magnetic DI plus sleeve gastrectomy achieved about 28% total weight loss and 66% excess weight loss at 6 months, reaching 34% total weight loss and 80% excess weight loss at 12 months in the small group followed that long (Surgical Endoscopy, 2023).
No anastomotic leaks in early studies. Across early reports, the magnet technique produced patent connections with no anastomotic leakage, bleeding, stricture, or device-related serious events — the main safety advantage over stapled/sutured bypass (Surgery for Obesity and Related Diseases, 2024; Surgical Endoscopy, 2023).
Rapid diabetes improvement. All patients with type 2 diabetes improved in early studies, with substantial drops in HbA1c and blood glucose (Surgery for Obesity and Related Diseases, 2024; Surgical Endoscopy, 2023).
Preserved absorption and fewer bowel side effects by design. Keeping partial flow through the normal path is intended to protect fat-soluble vitamin and micronutrient absorption and to reduce the diarrhea and bacterial overgrowth associated with fully diverting procedures (Obesity Surgery, 2024).
Durable metabolic benefit in early follow-up. A related self-forming-magnet bipartition (the SNAP procedure) showed sustained HbA1c and weight improvements out to 4 years (Obesity Surgery, 2026).
Who Is a Candidate
Based on the early study criteria, MagDI + SG has been offered to:
• Adults roughly 18–65 years old with a BMI of about 35–50 kg/m² (Surgery for Obesity and Related Diseases, 2024; Journal of Gastrointestinal Surgery, 2024).
In Dr. de la Cruz-Muñoz's practice, it is used mainly for patients with a BMI above 50 kg/m².
• Patients with type 2 diabetes seeking metabolic improvement (Surgical Endoscopy, 2023).
• Patients with a prior sleeve gastrectomy who need a second-stage procedure for inadequate weight loss or weight regain (the magnetic DI can be added after a previous sleeve) (Obesity Surgery, 2026; Surgery for Obesity and Related Diseases, 2024).
• People able and willing to commit to lifelong supplementation and follow-up, including the specific follow-up needed to confirm the anastomosis forms and the magnets pass (Surgical Endoscopy, 2023).
In the early trials, patients were generally excluded for type 1 or uncontrolled diabetes, injectable insulin use, prior intestinal/duodenal surgery, refractory GERD, large hiatal hernia, inflammatory bowel disease, implanted pacemaker or defibrillator (because of the magnets), pregnancy, or inability to follow the monitoring schedule (Surgical Endoscopy, 2023). Candidacy should be determined individually, and patients should understand this is an emerging procedure.
How the Procedure Is Performed
MagDI + SG is performed under general anesthesia using a combination of endoscopy (a scope passed through the mouth) and laparoscopy (small abdominal incisions). One magnet is delivered endoscopically to the first part of the duodenum, and a second magnet is guided to a loop of ileum about 250 cm from the end of the small intestine. With laparoscopic assistance, the two magnets are brought together and aligned side-to-side so they lock onto each other through the bowel walls. A sleeve gastrectomy is performed at the same time (in most cases), and the small opening between the two intestinal loops (Petersen's defect) is closed (Surgical Endoscopy, 2023; Journal of Gastrointestinal Surgery, 2024).
Over the next several days to weeks, the magnets compress the trapped tissue until a smooth new opening forms; the magnet pair is then expelled naturally through the digestive tract, typically around 6–7 weeks after surgery (median about 43–48 days) (Surgical Endoscopy, 2023; Journal of Gastrointestinal Surgery, 2024). Operative time for the combined procedure has averaged roughly 160–175 minutes, with a hospital stay of a few days (Obesity Surgery, 2026; Journal of Gastrointestinal Surgery, 2024).
To see how the magnets are placed and joined, watch our GT Metabolic Duodenoileostomy Animation.
Risks and Considerations
MagDI + SG is designed to reduce the risks of a conventional second anastomosis, and early studies reported no anastomotic leaks, bleeding, strictures, or device-related serious events (Surgical Endoscopy, 2023; Surgery for Obesity and Related Diseases, 2024). However, because experience is limited and follow-up is short, the full risk profile is not yet known. Potential and theoretical risks include:
• Risks of the sleeve gastrectomy component — leak at the staple line, bleeding, and acid reflux (Surgical Endoscopy, 2023).
• Most early adverse events were minor (Clavien-Dindo grade I–II); a small number of procedure-related serious adverse events occurred, but none were attributed to the magnet device itself (Surgery for Obesity and Related Diseases, 2024; Surgical Endoscopy, 2023).
• Uncertainty about long-term anastomosis patency — whether the magnet-formed connection stays open and functional over many years is a recognized open question that could affect long-term weight loss (Obesity Surgery, 2024).
• Nutritional deficiencies — any procedure that diverts intestinal flow carries a risk of vitamin and mineral deficiencies, so lifelong supplementation and monitoring are required, though the bipartition design aims to lessen this (Obesity Surgery, 2024; Cochrane Database of Systematic Reviews, 2026).
• Bowel-related effects — altered or looser stools are possible, though the preserved normal path is intended to reduce diarrhea and bacterial overgrowth (Obesity Surgery, 2024).
• Not for patients with implanted electronic cardiac devices because of the magnets (Surgical Endoscopy, 2023). (This contraindication is being studied.)
Recovery Timeline
Most patients stay in the hospital a few days and return to normal activity within a few weeks. Diet advances in stages — clear liquids, full liquids, pureed foods, then solids — under the guidance of the surgical and nutrition team. A distinctive feature of this procedure is that the new intestinal connection forms gradually over the weeks after surgery, and the magnets pass naturally around 6–7 weeks; follow-up imaging is used to confirm the anastomosis is patent and the magnets have been expelled (Surgical Endoscopy, 2023; Journal of Gastrointestinal Surgery, 2024). Lifelong daily vitamin and mineral supplements and a high-protein diet begin early.
Long-Term Expectations
Long-term data are not yet available for MagDI + SG. The best early evidence shows strong weight loss and metabolic improvement through 1 year, and a closely related self-forming-magnet bipartition (SNAP) has shown sustained HbA1c and weight benefit out to 4 years, with a modest weight-regain trend appearing by year 4 (Surgical Endoscopy, 2023; Obesity Surgery, 2026). Durability beyond this, and long-term anastomosis patency, remain under study (Obesity Surgery, 2024). Lifelong nutritional monitoring is essential, as with all duodenal-switch-type procedures.
Landmark Evidence
- First-in-human study: 15 adults with a BMI of 30–35 and type 2 diabetes had the duodeno-ileal connection formed by magnets. There were no leaks, bleeding, infections, strictures or deaths, all connections were open at one year, excess weight loss was 38.8%, and HbA1c fell from 8.2% to 6.6% (Gagner et al., Journal of the American College of Surgeons, 2025).
- Dr. de la Cruz-Muñoz's work: he lectures nationally on magnetic anastomosis, including "The Use of Magnets in Small Bowel Anastomoses" (2025) and "Throw Away Your Staplers, It's Time for Magnets!" at Cleveland Clinic (2025).
- What is still unknown: long-term weight, nutrition and durability data. MagDI should be considered an emerging procedure.
How It Compares
- Versus SADI-S: MagDI diverts only part of each meal and avoids a stapled or sewn intestinal connection, but SADI-S has far more long-term evidence.
- Versus sleeve alone: MagDI adds a metabolic bypass to the sleeve.
- Versus duodenal switch: MagDI is gentler on nutrition but less powerful.
More in Bariatric Surgery Procedures
Related procedures: Adjustable Gastric Band Surgery, Medical Weight Loss Program, Robotic Surgery, Sleeve Gastrectomy, Gastric Bypass, One-Anastomosis Gastric Bypass. For an overview of all options, see Bariatric Surgery.
Conditions treated: Obesity, Type 2 Diabetes, Sleep Apnea, Metabolic Dysfunction–Associated Steatohepatitis, Metabolic Syndrome, High Blood Pressure.
Why Choose Dr. de la Cruz-Muñoz
Dr. Nestor de la Cruz-Muñoz is a bariatric and metabolic surgeon whose outcomes are tracked through the national MBSAQIP quality program. He applies his high-volume experience, advanced minimally invasive techniques, and long-term metabolic support model with the goal of safe, effective, and compassionate care. He has been a pioneer in incorporating magnet technology into his practice. He was the second surgeon in the US to perform this procedure and has presented the technology at national and international conferences. He is currently the only surgeon in the world using the two magnetic systems available in his practice.
Dr. de la Cruz-Muñoz has been performing bariatric surgery for over 25 years and has completed more than 9,000 bariatric operations — a volume few surgeons reach.
Research and Publications
Dr. de la Cruz-Muñoz's published and presented work on this topic includes:
- Invited lecture: “The Use of Magnets in Small Bowel Anastomoses.” Caribbean Society of Endoscopic Surgeons, 2025.
- Invited lecture: “Throw Away Your Staplers, It’s Time for Magnets!” Innovations in Surgery, Cleveland Clinic, 2025.
Authored by Nestor de la Cruz-Muñoz, MD, FACS, DABOM. Last updated November 2026.
Total Body Weight Loss (TBWL) Expectations
Early data, from small studies with short follow-up:
- 6 months (concurrent MagDI + sleeve): ~28% TBWL (~66% excess weight loss) (Surgical Endoscopy, 2023).
- 12 months (concurrent, small group): ~34% TBWL (~80% excess weight loss) (Surgical Endoscopy, 2023).
- 1 year (magnet bipartition + sleeve): ~34% TBWL (Journal of Gastrointestinal Surgery, 2024).
- Revision after prior sleeve (6 months): ~7% TBWL (~17% excess weight loss) — much more modest when added to an existing sleeve (Surgery for Obesity and Related Diseases, 2024).
Longer-term weight-loss figures are not yet established. Individual results vary.
Expected Metabolic Improvements
- Type 2 diabetes: All patients with diabetes improved in early studies, with meaningful reductions in HbA1c and blood glucose; a related magnet bipartition sustained HbA1c improvement to 4 years (Surgical Endoscopy, 2023; Obesity Surgery, 2026).
- Other obesity-related conditions: Improvements in blood pressure, cholesterol, and sleep apnea are expected based on experience with similar duodenal-switch-type procedures, but have not yet been reported in large numbers specifically for MagDI (Surgery for Obesity and Related Diseases, 2024).
Weight Regain Prevention Strategy
As with all bariatric procedures, maintaining results depends on a high-protein diet, consistent daily supplementation, regular physical activity, and keeping all follow-up appointments. Because this is a newer, bipartition-type operation, confirming durable anastomosis patency is an added part of long-term monitoring (Obesity Surgery, 2024). If weight regain occurs, established revisional options (such as conversion to SADI-S or gastric bypass) remain available (Obesity Reviews, 2025).
GERD / Reflux Considerations
MagDI + SG includes a sleeve gastrectomy, which can contribute to acid reflux in some patients. The early studies specifically excluded patients with refractory GERD or a large hiatal hernia (Surgical Endoscopy, 2023). Patients with significant reflux require individualized evaluation, since gastric bypass is often preferred when reflux is the dominant problem.
Revision Options
The magnetic duodeno-ileostomy can itself be performed as a second-stage (revisional) procedure after a prior sleeve gastrectomy, though the added weight loss in that setting is more modest (Surgery for Obesity and Related Diseases, 2024; Obesity Surgery, 2026). If further revision is needed after MagDI + SG, conventional options — conversion to SADI-S, gastric bypass, or lengthening/adjusting the intestinal limb — remain available; among revisional procedures after sleeve, SADI-S ranks highest for weight loss in network meta-analyses (Obesity Reviews, 2025; World Journal of Surgery, 2024).
Body Composition & Muscle Preservation
Rapid weight loss carries a risk of losing muscle along with fat. Adequate protein intake (generally at least 60–80 g per day) combined with resistance exercise helps preserve lean muscle mass, and protein/albumin levels are monitored at follow-up — particularly important for any procedure with a malabsorptive component (Obesity Surgery, 2023).
Insurance & Qualification Requirements
Because MagDI + SG is an emerging procedure, insurance coverage is limited and many plans may consider it investigational. The sleeve gastrectomy component is widely covered when standard bariatric criteria are met (typically BMI ≥ 40, or ≥ 35 with an obesity-related condition, plus a supervised weight-management program and psychological evaluation). Our team verifies specific coverage and discusses options before scheduling.
Preparing for Surgery (Pre-Op Requirements)
- Complete nutritional, psychological, and medical evaluations.
- Baseline laboratory testing, including a full nutritional panel, and often an upper endoscopy to evaluate for hiatal hernia and reflux.
- Disclose any implanted electronic device (pacemaker/defibrillator), as this is a contraindication to the magnets (Surgical Endoscopy, 2023).
- Begin recommended dietary changes, stop smoking, and arrange long-term supplement supplies and follow-up support.
Post-Op Nutrition Overview
Lifelong supplementation is required, as with other duodenal-switch-type procedures. Typical regimens include daily multivitamins, fat-soluble vitamins (A, D, E, K), calcium citrate, iron, zinc, and vitamin B12, adjusted based on regular blood tests. The bipartition design — preserving partial flow through the normal intestinal path — is intended to improve absorption of fat-soluble vitamins and micronutrients compared with fully diverting procedures (Obesity Surgery, 2024). A high-protein diet of at least 60–80 g per day is essential.
Post-Op Activity & Exercise Guidance
Walking begins the day of surgery to reduce clot risk. Light activity resumes within the first week or two, with a gradual return to full exercise over 4–6 weeks. Once cleared, a combination of aerobic activity and resistance training supports muscle preservation and long-term weight maintenance.
Special Considerations for International Patients
International patients should plan to stay in Miami for approximately one week for MagDI with sleeve gastrectomy. Because this is a newer procedure, nutrition labs and follow-up are especially important; they can be done near home and reviewed virtually by our team. Please share your full medical history early so eligibility can be confirmed before travel.
Quick Procedure Details
Because this is a newer, often investigational procedure, coverage is limited and varies widely; some plans may cover the sleeve component but not the magnetic bypass. Our team manages pre-authorization, documentation, and benefit verification, and will discuss alternatives if coverage is not available.
Featured Procedures











Conditions












FAQ
Yes. Like SADI-S and duodenal switch, MagDI reduces absorption by bypassing part of the small intestine, so lifelong supplementation is required. A typical plan includes a bariatric multivitamin, calcium citrate, vitamin D and extra fat-soluble vitamins (A, D, E and K), along with B12 and iron as needed. Adequate daily protein is equally important. Regular lab tests — more often in the first year, then at least annually — check for deficiencies.
MagDI (magnetic duodeno-ileal anastomosis) is a newer metabolic operation that uses two magnets, placed endoscopically and laparoscopically, to gradually create a connection between the duodenum and the ileum without sutures or staples. It is typically combined with a sleeve gastrectomy, resulting in an operation similar in concept to SADI-S. It is designed to deliver strong weight loss and diabetes improvement with a potentially lower risk of leaks at the connection. Long-term data are still emerging.
Yes. Because the sleeve is the first component, MagDI can be added as a planned or revisional second stage without redoing the sleeve. Additional weight loss in that setting is more modest, about 8 kg at 6 months, since the original sleeve already produced much of the hormonal effect (Gagner et al., Surgery for Obesity and Related Diseases, 2024).
Three ways. MagDI uses magnets instead of staples or sutures to form the connection; the duodenum is left intact rather than divided; and food flows through two pathways (bipartition) instead of being fully rerouted. About 19% of a meal passes through the new magnetic connection while the rest follows the normal route (Cadiere et al., Journal of Gastrointestinal Surgery, 2024).
Early results are promising. MagDI combines a sleeve gastrectomy with a magnet-created duodeno-ileal connection, similar in concept to SADI-S, which is known for strong diabetes improvement. Bringing food to the lower intestine sooner increases GLP-1 and improves insulin sensitivity, and early studies report substantial improvements in blood sugar and reductions in diabetes medications. Because MagDI is a newer procedure, long-term data are still being collected.
MagDI is an emerging, largely investigational procedure. The first human cases were performed in late 2021, and current evidence comes from small prospective and multicenter studies with mostly one-year follow-up. Unlike the SADI-S and duodenal switch, it does not yet have established society endorsement or long-term durability data, so availability is limited and often study-based. Discuss current status directly with a bariatric program (Gagner et al., Surgery for Obesity and Related Diseases, 2024).
The conversion-specific data are early and modest: in the first multicenter study, patients who had a MagDI after a prior sleeve lost about 8 kg (17.4% excess weight loss) at six months, considerably less than patients who had a sleeve and MagDI together (Gagner et al., SOARD, 2024). Long-term conversion results are not yet established. For comparison, the conventional equivalent — conversion SADI-S — produces roughly 22–24% total weight loss maintained through five years (Esparham et al., SOARD, 2026).
It can, as with any procedure that bypasses part of the small intestine. MagDI creates a duodeno-ileal connection that reduces absorption, which drives weight loss and diabetes improvement but also increases the need for protein and vitamin monitoring. Most patients do well with lifelong supplements, adequate protein and regular labs. When malnutrition or persistent diarrhea develops despite these measures, revision to lengthen the common channel or reverse the bypass can restore absorption.
All bariatric operations have metabolic benefits, but gastric bypass, SADI-S, MagDI and duodenal switch produce the strongest effects on diabetes, insulin resistance and cholesterol because they reroute the intestine and change gut hormones more profoundly. Sleeve gastrectomy also improves metabolic disease. The best choice depends on your diabetes severity, BMI, reflux and willingness to follow nutritional monitoring.
Early results suggest weight loss similar to SADI-S, with many patients losing roughly 65–80% of excess weight, along with improvements in diabetes and other metabolic conditions. MagDI is a newer procedure, so long-term results are still being collected. When used as a revision after a sleeve, it can provide meaningful additional weight loss. Lifelong vitamins and lab monitoring are required.