SADI-S (Single-Anastomosis Duodeno-Ileal Bypass with Sleeve)

Overview
At a Glance
- What it is: A sleeve gastrectomy plus a single connection between the duodenum and the ileum, preserving the pylorus
- Who it is for: Recommended by the 2022 ASMBS/IFSO guidelines for adults with a BMI of 35 or higher, and considered at a BMI of 30–34.9 with metabolic disease (27.5 or higher for people of Asian descent) (Eisenberg et al., Surgery for Obesity and Related Diseases, 2022). Especially considered for higher BMI and severe type 2 diabetes
- Results: Greater weight loss than gastric bypass in a randomized trial (see Benefits and Landmark Evidence below)
- Main trade-off: Lifelong vitamin and mineral supplements and regular labs are essential
- Hospital stay and recovery: Usually one to two nights; desk work in about two weeks
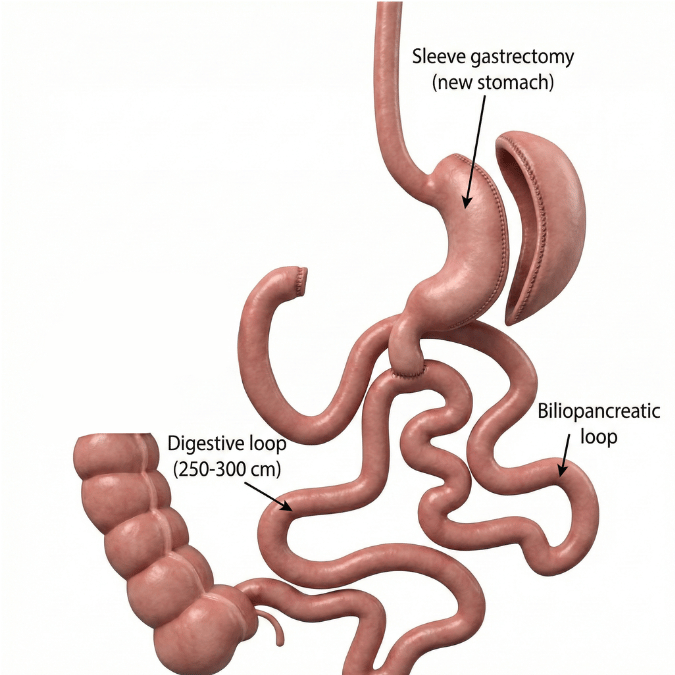
SADI-S (single-anastomosis duodeno-ileal bypass with sleeve gastrectomy) was introduced in 2007 as a simplified evolution of the biliopancreatic diversion with duodenal switch (BPD/DS). It combines a sleeve gastrectomy with a single intestinal bypass (one anastomosis instead of two), which shortens operating time and reduces the risks of leak, anastomotic stricture, and internal hernia — while preserving the strong weight-loss and metabolic benefits of the duodenal switch (Obesity Surgery, 2024; Obesity Surgery, 2025).
Since 2020, both the International Federation for the Surgery of Obesity and Metabolic Disorders (IFSO) and the American Society for Metabolic and Bariatric Surgery (ASMBS) have formally recognized SADI-S as a standard metabolic and bariatric procedure (Obesity Surgery, 2024; Obesity Surgery, 2026). Because it keeps the pylorus (the natural stomach-outlet valve) intact, SADI-S avoids the marginal ulcers, bile reflux, and dumping syndrome associated with some other bypass operations (Obesity Surgery, 2025; Obesity Surgery, 2021).
To learn how SADI-S is offered at our Miami practice, and who is a good candidate for it, see SADI-S Surgery in Miami, FL.
How the Procedure Works
SADI-S produces weight loss and metabolic improvement through three mechanisms:
• Restriction: The sleeve-shaped stomach holds much less food, so meals feel satisfying with smaller portions (Obesity Surgery, 2021).
• Malabsorption: A single connection between the duodenum (just past the preserved pylorus) and a loop of ileum reroutes food so that digestive juices mix with it only in a shortened common channel — typically 250–300 cm from the ileocecal valve — reducing calorie and fat absorption (Obesity Surgery, 2024; Obesity Surgery, 2018).
• Hormonal/metabolic change: Rerouting nutrients to the lower intestine, along with a longer biliopancreatic limb and favorable changes in gut hormones and bile acids, improves blood-sugar control — often rapidly and before major weight loss (Obesity Surgery, 2025).
Benefits
Greater weight loss than gastric bypass. In the randomized SADISLEEVE trial, SADI-S produced significantly higher excess weight loss than Roux-en-Y gastric bypass at 2 years (76.0% vs 68.1% EWL), with a similar safety profile (Lancet, 2025).
Higher diabetes remission. Pooled data from over 4,600 patients show significantly greater total weight loss, excess weight loss, and type 2 diabetes remission with SADI-S compared with gastric bypass (Obesity Surgery, 2025).
Technically simpler and safer than classic duodenal switch. The single anastomosis shortens operative time and reduces the risks of leak, stricture, and internal hernia (Obesity Surgery, 2025; Obesity Surgery, 2024).
Pylorus preservation. Keeping the pylorus lowers the risk of marginal ulcers, bile reflux, and dumping syndrome (Obesity Surgery, 2025).
Durable results. Long-term single-center data report roughly 38% total weight loss at 5 years and 34% at 10 years (Obesity Surgery, 2025; Obesity Surgery, 2022).
Who Is a Candidate
SADI-S is generally best suited for:
• Adults with a high BMI (often ≥ 45–50 kg/m²) who need powerful, durable weight loss (Obesity Surgery, 2022).
• Patients with severe or difficult-to-control type 2 diabetes, including insulin-treated diabetes, regardless of BMI in some protocols (Obesity Surgery, 2022; Scientific Reports, 2024).
• Patients needing a more powerful operation after an inadequate response to a prior sleeve gastrectomy (second-stage or conversion procedure) (Obesity Surgery, 2026).
• People able and willing to commit to lifelong supplementation and regular follow-up blood tests (Obesity Surgery, 2024).
General candidacy follows standard bariatric thresholds: BMI ≥ 40, or ≥ 35 with an obesity-related condition, or 30–34.9 with inadequately controlled type 2 diabetes, adjusted for ethnicity (Clinical Practice Guidelines, ASMBS/AACE, 2020). SADI-S is generally not recommended for patients with inflammatory bowel disease, chronic diarrhea, or those unlikely to maintain close nutritional follow-up (Obesity Surgery, 2024).
How the Procedure Is Performed
SADI-S is performed under general anesthesia using minimally invasive (laparoscopic or robotic) techniques through several small incisions. It has two components usually done in one operation: a sleeve gastrectomy with the pylorus preserved, followed by a single anastomosis connecting the first part of the duodenum to a loop of ileum, leaving a common channel of 250–300 cm. Because there is only one intestinal connection and no mesenteric division, operative time and certain technical risks are reduced (Obesity Surgery, 2024; Obesity Surgery, 2025). Most patients stay in the hospital 1–2 nights, and in selected low-risk patients it has been performed as an outpatient procedure (Obesity Surgery, 2025).
Risks and Considerations
SADI-S is considered safe and reproducible, with low early-complication rates, but it carries the nutritional risks inherent to malabsorptive surgery (Obesity Surgery, 2024).
- Early complications are uncommon: pooled reoperation, bleeding, and anastomotic leak rates of roughly 3.1%, 1.1%, and 0.9%, respectively (Obesity Surgery, 2024). In the SADISLEEVE trial, serious surgical adverse events were comparable to gastric bypass, though severe diarrhea was more frequent after SADI-S (Lancet, 2025).
- Nutritional deficiencies are the most important long-term risk, especially fat-soluble vitamins (A, D, E, K), iron, and protein. Reported ranges are wide — for example, vitamin D deficiency 24–62%, vitamin A deficiency up to ~45%, iron/ferritin deficiency 10–67%, and protein/albumin deficiency up to ~17–41% depending on common-channel length and supplementation (Obesity Surgery, 2023; Scientific Reports, 2024).
- Bowel-related effects, including more frequent, loose, or foul-smelling stools and excess gas from fat malabsorption (Obesity Surgery, 2024).
- Protein malnutrition and, rarely, the need for surgical revision (e.g., lengthening the common channel) for severe malnutrition or excessive weight loss (ASMBS, 2026).
A shorter common channel (200 cm) increases nutritional risk; the now-standard 250–300 cm channel was adopted to reduce deficiencies (Obesity Surgery, 2024; Scientific Reports, 2024).
Recovery Timeline
Most patients return to normal activity within a few weeks. Diet advances in stages — clear liquids, full liquids, pureed foods, then solids — over several weeks under the guidance of the surgical and nutrition team. Lifelong daily vitamin and mineral supplements begin right away, along with a high-protein diet (typically at least 60–80 g per day) (Obesity Surgery, 2023; Scientific Reports, 2024).
Long-Term Expectations
Weight loss reaches its peak within the first 1–2 years and is well maintained long term. Long-term single-center data report excess weight loss and total weight loss of roughly 87% and 38% at 5 years and 80% and 34% at 10 years (Obesity Surgery, 2025; Obesity Surgery, 2022). Lifelong annual nutritional blood tests are essential to safe, durable success (Obesity Surgery, 2024).
Landmark Evidence
- After prior bariatric surgery: in patients converted after a failed band, a single-anastomosis duodenal switch produced greater weight loss than sleeve conversion, and the prior operation did not blunt its effect (Pearlstein et al., Obesity Surgery, 2019).
- Why limb length matters: in malabsorptive operations, shorter absorptive lengths are linked to severe protein-energy malnutrition (systematic review and meta-analysis, Annals of Surgery, 2021), which is why SADI-S keeps a long common channel.
- Survival: Across 17 studies and more than 174,000 people, metabolic and bariatric surgery was associated with a 49% lower risk of death and a median of 6.1 additional years of life compared with non-surgical care. The benefit was greatest in people with type 2 diabetes (Syn et al., The Lancet, 2021).
How It Compares
- Versus duodenal switch: one connection instead of two and a longer common channel, so it is simpler and gentler on nutrition, with slightly less effect.
- Versus gastric bypass: more powerful for weight and diabetes and preserves the pylorus, but carries greater nutritional demands and a sleeve that may cause reflux.
- Versus MagDI: MagDI diverts only part of each meal through a magnet-formed connection and is still emerging.
More in Bariatric Surgery Procedures
Related procedures: Duodenal Switch, Magnetic Duodeno-Ileal Bypass with Sleeve, Adjustable Gastric Band Surgery, Medical Weight Loss Program, Robotic Surgery, Sleeve Gastrectomy. For an overview of all options, see Bariatric Surgery.
Conditions treated: Obesity, Type 2 Diabetes, Sleep Apnea, Metabolic Dysfunction–Associated Steatohepatitis, Metabolic Syndrome, High Blood Pressure.
Why Choose Dr. de la Cruz-Muñoz
Dr. Nestor de la Cruz-Muñoz is a bariatric and metabolic surgeon whose outcomes are tracked through the national MBSAQIP quality program. He applies his high-volume experience, advanced minimally invasive techniques, and long-term metabolic support model with the goal of safe, effective, and compassionate care.
SADI-S is a precise malabsorptive operation, and results depend on surgical judgment. Dr. de la Cruz-Muñoz has over 25 years of bariatric surgery experience and more than 9,000 bariatric operations, a volume few surgeons reach.
Whether you live nearby or are coming from out of state, practical information on scheduling, surgery and aftercare is on our SADI-S surgery in Miami page.
Authored by Nestor de la Cruz-Muñoz, MD, FACS, DABOM. Last updated November 2026.
Total Body Weight Loss (TBWL) Expectations
• 1 year: ~40% TBWL (excess weight loss consistently above 60%) (Obesity Surgery, 2021).
• 2 years: superior to gastric bypass — 76.0% vs 68.1% excess weight loss in a randomized trial (Lancet, 2025).
• 5 years: ~38% TBWL (Obesity Surgery, 2025; Obesity Surgery, 2022).
• 10 years: ~34% TBWL (Obesity Surgery, 2025).
Individual results vary with starting weight, common-channel length, diet, and adherence to follow-up.
Expected Metabolic Improvements
Type 2 diabetes: Remission in roughly 70–73% of patients, significantly higher than gastric bypass, and durable even in advanced, insulin-treated diabetes (Obesity Surgery, 2025; Obesity Surgery, 2021).
Dyslipidemia: Improvement or resolution in roughly 77% of patients (Obesity Surgery, 2021).
Hypertension: Resolution in roughly 59% of patients; similar to gastric bypass (Obesity Surgery, 2021; Obesity Surgery, 2024).
Obstructive sleep apnea: High rates of improvement or resolution (Obesity Surgery, 2024).
Weight Regain Prevention Strategy
SADI-S has a relatively low weight-regain rate because of its malabsorptive component, but maintaining results still depends on a high-protein diet, consistent daily supplementation, regular physical activity, and keeping all follow-up appointments so nutrition and weight trends are caught early (Obesity Surgery, 2024). When significant regain occurs after other procedures, conversion to SADI-S is itself an effective revisional option, adding meaningful additional weight loss (Obesity Surgery, 2026).
GERD / Reflux Considerations
Because SADI-S preserves the pylorus, it avoids the bile reflux seen with some single-anastomosis bypasses. Because it is built on a sleeve, however, it does not correct acid reflux and can contribute to it in some patients. Patients with significant or medication-resistant GERD need individualized evaluation and are usually better served by gastric bypass (Obesity Surgery, 2025).
Revision Options
SADI-S is commonly used as a second-stage or conversion procedure after an inadequate response to sleeve gastrectomy or other operations, producing durable additional weight loss (Obesity Surgery, 2026; Obesity Surgery, 2026). If a patient develops severe malnutrition, hypoalbuminemia, or excessive weight loss after SADI-S, the common channel can be lengthened or the anatomy revised (ASMBS, 2026). Overall revision rates are low, but lifelong monitoring helps catch problems early.
Body Composition & Muscle Preservation
Rapid, large weight loss carries a risk of losing muscle along with fat, and the malabsorptive nature of SADI-S makes adequate protein intake especially important. A protein target of at least 60–80 g per day, combined with resistance exercise, helps preserve lean muscle mass. Protein and albumin levels are monitored at every follow-up visit, since hypoalbuminemia is a recognized risk (Obesity Surgery, 2023; Scientific Reports, 2024).
Insurance & Qualification Requirements
Most insurers require documentation of a qualifying BMI (typically ≥ 40, or ≥ 35 with obesity-related conditions), a medically supervised weight-management program, and nutritional and psychological evaluation. Because SADI-S is a newer procedure, some plans may require additional documentation or may not yet cover it; our team verifies specific coverage before scheduling (Clinical Practice Guidelines, ASMBS/AACE, 2020).
Preparing for Surgery (Pre-Op Requirements)
Complete nutritional, psychological, and medical evaluations (Obesity Surgery, 2022).
Baseline laboratory testing, including a full nutritional panel, and often an upper endoscopy (Obesity Surgery, 2022).
Begin dietary changes and any recommended pre-operative weight loss.
Stop smoking and arrange for long-term supplement supplies and follow-up support.
Post-Op Nutrition Overview
Lifelong supplementation is mandatory after SADI-S. Typical regimens include daily multivitamins, high-dose fat-soluble vitamins (A, D, E, K), calcium citrate, iron, zinc, and vitamin B12, with doses adjusted based on regular blood tests (Obesity Surgery, 2023). A high-protein diet of at least 60–80 g per day is essential. Even with careful supplementation, deficiencies can occur and require ongoing monitoring and dose adjustments (Scientific Reports, 2024).
Post-Op Activity & Exercise Guidance
Walking begins the day of surgery to reduce clot risk. Light activity resumes within the first week or two, with a gradual return to full exercise over 4–6 weeks. Once cleared, a combination of regular aerobic activity and resistance training supports muscle preservation and long-term weight maintenance.
Special Considerations for International Patients
SADI-S patients from abroad should plan to stay in Miami for approximately one week. Before you travel, our team confirms that bariatric vitamins and lab testing are available near you. Follow-up visits are virtual, and lab results from home are reviewed for life.
Quick Procedure Details
Most major insurers cover SADI-S when medical criteria are met. Our team verifies benefits, obtains authorizations, and guides patients through the insurance process.
Featured Procedures












Conditions









FAQ
Coverage depends on your plan and the procedure. Medically necessary operations — such as hernia repair, gallbladder removal, anti-reflux surgery, myotomy for achalasia and cancer surgery — are generally covered, subject to your deductible and coinsurance. Bariatric surgery is covered by many plans when you meet their criteria, though some employers exclude it, and newer procedures such as SADI-S may require additional review. Endoscopic weight-loss procedures are often self-pay. Our office verifies your benefits and handles prior authorization before surgery.
Yes. Lifelong supplementation is required after SADI-S because part of the small intestine is bypassed, reducing absorption of fat-soluble vitamins, calcium, iron and protein. Requirements are usually somewhat less intensive than after a duodenal switch but greater than after a sleeve. A typical plan includes a bariatric multivitamin, calcium citrate, vitamin D, extra vitamins A, E and K as needed, and regular labs.
SADI-S (single-anastomosis duodeno-ileal bypass with sleeve gastrectomy) combines a sleeve gastrectomy with one intestinal connection between the duodenum and a lower part of the small intestine (the ileum). It is a simplified version of the duodenal switch with one connection instead of two, offering strong weight loss and diabetes remission. It is often used for higher BMIs and as a second step after a sleeve.
Three ways. MagDI uses magnets instead of staples or sutures to form the connection; the duodenum is left intact rather than divided; and food flows through two pathways (bipartition) instead of being fully rerouted. About 19% of a meal passes through the new magnetic connection while the rest follows the normal route (Cadiere et al., Journal of Gastrointestinal Surgery, 2024).
Yes. SADI-S has short-term safety comparable to gastric bypass, and because it uses a single intestinal connection, it is simpler than a traditional duodenal switch.
Because SADI-S reduces absorption of some nutrients, it requires lifelong vitamin and mineral supplements and regular lab monitoring. Patients who stay in follow-up and take their supplements generally do very well.
Yes. SADI-S strongly improves insulin resistance and leads to diabetes remission in many patients, with results similar to the duodenal switch. Delivering food to the lower intestine sooner boosts GLP-1 and other gut hormones, and significant weight loss improves insulin sensitivity. It is particularly considered for patients with higher BMIs or more advanced diabetes.
Most patients lose a large share of their excess weight after SADI-S, with durable results. It is especially effective for people with a high BMI and as a revision after sleeve gastrectomy. Because it is more malabsorptive than a sleeve or gastric bypass, lifelong vitamins, adequate protein and regular lab monitoring are essential.
There is no single best operation. The choice depends on your BMI, whether you have reflux or a hiatal hernia, how severe your diabetes is, your eating patterns, prior surgeries and long-term goals. Sleeve gastrectomy and gastric bypass are the most common procedures. Gastric bypass is preferred for significant reflux. SADI-S and duodenal switch offer the greatest weight loss and diabetes control for higher BMIs, with a greater need for vitamin monitoring. Your surgeon will recommend the best fit after a full evaluation.
The duodenal switch is often recommended for patients with a very high BMI (typically 50 or more), those with severe or long-standing type 2 diabetes, and patients who have regained weight after a sleeve gastrectomy. Good candidates are committed to lifelong vitamin supplements, adequate protein and regular lab follow-up. It is generally not the best choice for patients with significant reflux or chronic diarrhea. SADI-S, a simplified version, may be considered for similar goals.
All bariatric operations have metabolic benefits, but gastric bypass, SADI-S, MagDI and duodenal switch produce the strongest effects on diabetes, insulin resistance and cholesterol because they reroute the intestine and change gut hormones more profoundly. Sleeve gastrectomy also improves metabolic disease. The best choice depends on your diabetes severity, BMI, reflux and willingness to follow nutritional monitoring.
SADI -S offers powerful long -term fat loss, similar to DS.
Yes — lifelong supplementation is required after SADI-S. Because part of the small intestine is bypassed, patients need a bariatric multivitamin, calcium citrate, vitamin D and often extra fat-soluble vitamins (A, E and K), plus iron and B12 as needed. Adequate daily protein is equally important. Labs are checked regularly in the first year and at least annually afterward.
Most patients return to normal daily activities within two to three weeks after SADI-S. Hospital stays are usually one to two nights. Desk work typically resumes in about two to three weeks and physical work in about six weeks, with structured exercise beginning at four to six weeks. The diet advances in stages over several weeks.