

Why Am I Still Tired After Bariatric Surgery?

Quick Answer
Watch Related Video
Article
Why Am I Still Tired After Bariatric Surgery? 6 Measurable, Treatable Causes of Post-Op Fatigue
The exhaustion you feel months after surgery is not your new normal, and it is not something to automatically write off as "recovery." Patients are often told to be patient and wait it out. But when fatigue drags on, it is usually a sign that something measurable is going on: iron, B12, thiamine, protein, sleep, thyroid, or a mood problem that has not been screened for.
This matters because the deficiency making you tired today could, if left untreated, lead to permanent nerve damage, bone loss, or strain on your heart (Mechanick et al., Obesity, 2020). Fatigue is a symptom, and symptoms have causes we can test for, identify, and treat.
Here is the one reassuring fact to hold onto: in almost every case, there is an answer, and it is something that can be treated.
First, What Counts as "Normal" Fatigue?
In the first week after surgery you are living on roughly 400 calories a day. By weeks three and four that rises to about 600 to 800. Some tiredness in those early weeks is almost guaranteed, and it usually eases as your intake increases and your body shifts into fat-burning. That is normal fatigue, and it has a limited run.
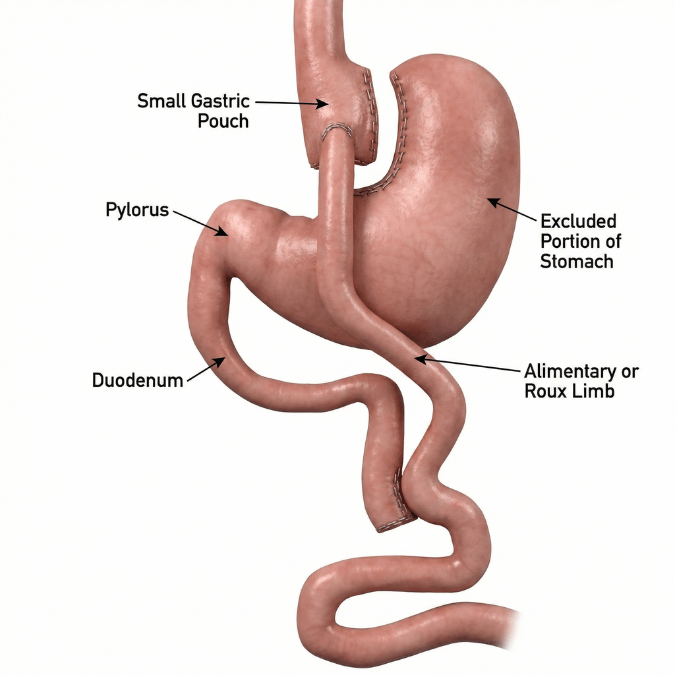
The fatigue that deserves attention is exhaustion that lasts for months, or that shows up later and gets worse instead of better. That is often your body telling you something has run low, because the same surgery that reduces your hunger can also reduce your ability to pull nutrients from food.
These deficiencies are not rare. Anemia can affect as many as a third to half of patients within two years of gastric bypass or duodenal switch. Iron deficiency becomes more common over time. Vitamin D can be low in anywhere from a third to three-quarters of patients (Mechanick et al., Obesity, 2020). Almost every one of these can show up first, and sometimes only, as fatigue.
The best way to work through it is to think in lanes. Each cause has its own pathway, its own test, and its own treatment.
Lane 1: The Blood-Building Nutrients (Iron, B12, Folate, Copper, Selenium)
Low blood counts and reduced oxygen delivery to your tissues are among the most common drivers of post-op exhaustion. A frequent mistake, even among good doctors, is finding a low blood count, prescribing iron, and moving on. Five different nutrients can contribute to anemia after surgery, and each does it for a different reason.
Iron is the single most common deficiency behind fatigue after surgery, and it grows over time. In a large cohort, iron deficiency affected about 14 percent of patients at one year and 26 percent at three years, reaching roughly 35 to 38 percent after gastric bypass (Nuzzo et al., Lancet Gastroenterology and Hepatology, 2021). Three reasons stack up: iron is absorbed mainly in the duodenum that bypass routes around, stomach acid needed to absorb it is reduced, and surgical connections can develop ulcers that bleed slowly. Gastroenterology guidance treats new iron deficiency after bypass as a reason to consider endoscopy to look for a bleeding ulcer. After bypass, oral iron pills often do not work well, and intravenous iron is frequently needed. Take oral iron with vitamin C, and keep it separate from calcium, acid reducers, and tea.
Vitamin B12 can cause both anemia and nerve damage, producing a heavy fatigue with numbness and brain fog. The most important point is how it is tested: a "normal" serum B12 does not always rule out deficiency, which is why clinicians may check methylmalonic acid (MMA) when symptoms suggest a problem (Mechanick et al., Obesity, 2020). Metformin, proton pump inhibitors, and nitrous oxide can all lower B12.
Folate can cause the same large-cell anemia as low B12 and is linked to low mood and mental fog. Critically, high-dose folate can mask a B12 deficiency, improving the blood count while nerve damage silently progresses, so routine folate is kept modest and B12 is checked alongside it.
Copper deficiency is easy to miss and can mimic B12 deficiency almost exactly, causing anemia and nerve damage with an unsteady walk and tingling. A preventable cause everyone should know: too much zinc depletes copper. Patients who start zinc for post-op hair loss can unknowingly drive copper too low.
Selenium is considered when the usual tests do not explain ongoing fatigue, unexplained anemia, persistent diarrhea, or a heart-muscle problem, particularly after malabsorptive procedures.
The takeaway: anemia is not one thing. Sorting out which nutrient applies is what points to the right treatment.
Lane 2: Thiamine (Vitamin B1) and the Emergency Lane
This is the lane that worries clinicians most. Iron, B12, and copper deficiencies develop gradually. Thiamine deficiency can move from mild to permanent brain injury within weeks, because the body stores only about two to three weeks' worth (Nuzzo et al., Lancet Gastroenterology and Hepatology, 2021).
Pooled studies put thiamine deficiency at roughly 27 percent after bariatric surgery, and it has been documented as early as eight to fifteen weeks post-op (Bahardoust et al., Obesity Surgery, 2022). The biggest warning sign is repeated vomiting, which has been reported in about 90 percent of people who develop the dangerous form. A diuretic such as furosemide can increase thiamine loss.
Untreated, thiamine deficiency can progress to Wernicke encephalopathy, a true brain injury. The classic triad is confusion, abnormal eye movements, and an unsteady walk, but most patients never show all three. Waiting for the full triad means waiting too long. Of those who develop Wernicke encephalopathy without treatment, up to 20 percent die, and up to 85 percent of survivors develop the permanent memory loss of Korsakoff syndrome (Yu et al., Obesity Surgery, 2023).
The single most important safety rule for any patient or provider: thiamine must be given before or alongside intravenous glucose, never sugar first. Giving glucose to a thiamine-depleted patient can burn through the last reserves and trigger Wernicke encephalopathy in the emergency room (Oudman et al., Obesity Surgery, 2018). Diagnosis is clinical, because brain imaging can look normal in up to half of true cases, so treatment is started on suspicion.
The fix is cheap and fast. Every post-op patient should take at least 12 mg of thiamine daily, ideally 50 mg from a B-complex or high-potency multivitamin. Anyone who is vomiting needs injected thiamine without waiting for test results, and suspected Wernicke encephalopathy is treated with high-dose IV thiamine. Magnesium is given alongside, because thiamine cannot work without it.
Lane 3: Protein and Muscle
Rapid weight loss does not take only fat. The average patient loses more than eight kilograms of fat-free mass in the first year, and up to 70 percent of that muscle loss happens in the first three to six months, exactly when intake and protein are lowest (Nuijten et al., Obesity Surgery, 2023). Because muscle is metabolically active, losing it lowers your resting metabolic rate and can leave you feeling sluggish.
Protein is the most serious macronutrient to get right, and it is hard to eat after surgery. The target is at least 60 grams a day, and often 1 to 1.5 grams per kilogram of ideal body weight, yet average intake in the early months can be closer to 45 grams (Mechanick et al., Obesity, 2020). Prioritize protein at every meal before other foods, and use a liquid supplement if food alone falls short.
Protein supplies the building blocks, but resistance training signals that the muscle is still needed. Supervised exercise reduces fat-free mass loss, and combined aerobic plus resistance programs preserve more muscle than no structured exercise (Lamarca et al., Obesity Surgery, 2021). Start walking as soon as you are cleared, then add light full-body strength training two to three times a week once your surgeon approves, usually around four to six weeks.
Lane 4: Post-Bariatric Hypoglycemia
This fatigue comes on suddenly, usually one to three hours after a meal high in carbohydrates: shaky, sweaty, foggy, with a pounding heart and a sense of hitting a wall. After surgery, food reaches the small intestine quickly, driving a sharp blood-sugar rise, an amplified hormone and insulin response, and then a crash (Sandoval and Patti, Nature Reviews Endocrinology, 2023).
It is worth distinguishing early dumping, which happens within about 10 to 60 minutes with nausea, cramping, and flushing, from true post-meal low blood sugar, which comes later. Clearly symptomatic post-bariatric hypoglycemia is estimated at around 10 to 30 percent of patients, more common after bypass and in people who did not have diabetes before surgery. A key timing clue sets it apart: it usually develops a year or more after surgery, sometimes as late as five years out, so patients often never connect the afternoon crashes to their operation.
Most people can manage it with diet alone: cut simple sugars, keep carbohydrate portions modest, pair carbs with protein and fat, and eat smaller meals every three to four hours. If diet is not enough, acarbose with meals is the usual first medication, with more specialized options reserved for harder cases and an endocrinologist involved. Removing part of the pancreas is no longer recommended, as hypoglycemia returns in about 90 percent of cases.
Lane 5: Sleep and Sleep Apnea
Bariatric surgery is one of the most effective treatments we have for obstructive sleep apnea. The average patient's apnea-hypopnea index often falls from around 39 events per hour to around 12 after surgery (Arterburn et al., JAMA, 2020). But improvement is not the same as cure: in detailed follow-up, severity stayed about the same in roughly 41 percent of patients and fully resolved in only about 16 percent.
So if you had significant sleep apnea before surgery, lost a lot of weight, and assumed it was gone, it may still be there, and residual sleep apnea is a powerful, easy-to-miss cause of daytime fatigue. If you snore, wake unrefreshed, or feel sleepy during the day, ask your care team about repeat testing. You may still need CPAP or an adjustment to your pressure settings.
Lane 6: Mood and Mental Health
This lane may be the most important and the most overlooked. The bariatric population carries a higher burden of depression and anxiety than the general public, often long before surgery. Mood usually lifts dramatically in the first year, but that improvement is not guaranteed to last, and scores can drift back toward baseline over the following years (Yin et al., Scientific Reports, 2025).
Timing is why this fatigue goes unrecognized. In one month-by-month study, anxiety and sleep quality improved right away, but depression scores were actually higher at three months than before surgery, with lasting improvement not appearing until after thirteen months (Yin et al., Scientific Reports, 2025). Chronic anxiety is physically draining, disordered eating patterns both exhaust you and worsen nutrition, and night-eating patterns wreck sleep quality.
Mental health care should not end when the post-surgery honeymoon does. Stay connected with a mental health professional just as you would with your dietitian. Cognitive behavioral therapy helps anxiety, and medication is an effective, appropriate treatment for moderate to severe depression. If fatigue comes with low mood, loss of interest, relentless anxiety, eating that feels out of control, or sleep that never leaves you rested, that is a medical part of recovery, every bit as real as your iron level.
The Roadmap: What to Check First
- Get your blood drawn. Labs are step one, not step five. Consider a complete blood count, comprehensive metabolic panel, iron studies with ferritin, B12, folate, and vitamin D, plus thiamine, zinc, copper, and parathyroid hormone depending on your procedure and symptoms. Routine follow-up labs matter: every three months in the first year, then at least yearly for life.
- The emergency exception. Ongoing vomiting with fatigue, tingling, confusion, balance problems, or vision changes needs urgent evaluation for thiamine deficiency, treated before results return.
- Watch the clock. Fatigue that crashes one to three hours after eating and improves with food points to post-bariatric hypoglycemia, which you can start managing at the table.
- Audit protein and activity. Aim for your team's protein target and build toward regular strength training.
- Reassess sleep. Do not assume weight loss cured your sleep apnea.
- Check in on mental health. Screening should continue well beyond the first year.
The most important takeaway: fatigue after bariatric surgery is not the price of admission. Treat it as a clue, not a verdict. Get the blood work, keep your appointments, and work through the plan with your care team.
Further Information
For additional context and a deeper professionalperspective, you can read the companion LinkedIn article linked below.
Medical Topics Covered


Dr. de la Cruz‑Muñoz specializes in advanced minimally invasive and robotic surgery, metabolic disease management, and comprehensive long‑term patient care. His work integrates clinical expertise, academic leadership, and a commitment to evidence‑based medicine. He has trained surgeons across the country, contributed to national guidelines, and is widely regarded for his outcomes, innovation, and patient‑centered approach.
Patients choose Dr. de la Cruz‑Muñoz for his combination of surgical excellence, metabolic expertise, and lifelong dedication to improving patient health through compassionate, high‑quality care.
Procedures We Offer




Conditions
FAQ
Some fatigue in the first few weeks is expected while calorie intake is very low. But exhaustion that lasts for months, or that appears later and worsens, is not something to simply wait out. It usually points to a measurable cause such as a nutrient deficiency, low protein and muscle, blood-sugar crashes, residual sleep apnea, or depression, all of which can be identified and treated (Mechanick et al., Obesity, 2020).
A reasonable panel includes a complete blood count, a comprehensive metabolic panel, iron studies with ferritin, vitamin B12, folate, and vitamin D, with thiamine, zinc, copper, and parathyroid hormone added based on your procedure and symptoms. Importantly, a "normal" serum B12 does not always rule out deficiency, so methylmalonic acid may be checked when nerve symptoms are present (Mechanick et al., Obesity, 2020). Follow-up labs are recommended every three months during the first year and at least yearly thereafter.
People Also Ask
Obesity is recognized as a chronic metabolic disease influenced by genetics, hormones, environment, and biological factors — not simply lifestyle choices.
The body has built-in mechanisms that defend weight, including hunger hormones and metabolic adaptations that make long-term weight loss challenging.
Yes. Genetics can significantly influence body weight regulation, appetite, metabolism, and an individual's susceptibility to obesity.
GLP-1 medications help regulate appetite, slow stomach emptying, improve satiety, and support sustainable weight management.
Yes. Obesity is associated with conditions such as Type 2 diabetes, hypertension, sleep apnea, fatty liver disease, and cardiovascular disease.
Dieting alone often cannot overcome the biological adaptations that increase hunger and decrease energy expenditure after weight loss.
Medical evaluation may be appropriate when excess weight affects health, quality of life, or contributes to obesity-related medical conditions.
Yes. Bariatric surgery addresses biological and metabolic factors involved in obesity and can lead to significant long-term health improvements.


